Type IV RTA
1.Pathophysiology#
- Due to aldosterone resistance or aldosterone↓
- Causing non-AG metabolic acidosis and hyperkalemia
- For non-AG metabolic acidosis mechanism
- (主因)1.Hyperkalemia->p. tubules intracellular alkalosis->↓NH3產生(↓glutamine, glutamate deamination) and ↓bicarbonate reabsorption(核心本質為高血鉀引發之近端產銨障礙,集尿管排酸功能多保留且尿 pH 常可 <5.3;治療首要為「降血鉀」,血鉀正常化後產銨能力與酸中毒常隨之改善)
- 註:反之, Proximal tubules在acidosis時(also when hypokalemia-->intracellular acidosis)會↑glutamine deamination而↑NH3, NH4+ production; NHE3可function as Na-NH4+ exchanger; NH3也可直接穿過apical membrane到lumen中
- 2.正常medullary TAL會再吸收NH4+(by NKCC2 transporter and KCC, which could function as Na-NH4+-CC2 transporter and NH4Cl cotransporter), 而在medullary collecting duct分泌出來; hyperkalemia時競爭之下TAL K吸收較多, NH4+吸收較少(這樣不是lumen中更多??還是因為↓medullary collecting duct分泌?所以局部濃度of medullary collecting duct↓, 不過主要還是因為p. tubules製造NH3↓), 使interstitial NH4+ concentration↓
- 3.在collecting duct, basolateral Na-K-ATPase可function as Na-NH4+ exchanger, 排出NH4+, 但K會競爭此function, 再加上hypoaldosterone時cells內Na較低(?)(因為↓ENaC?)且interstitial NH4+ concentration↓, 因此減少NH4+ secretion
- 註:NH4+經apical membrane的ROMK or RhCG到lumen中
- 4.Aldosterone↓, 也直接↓type A intercalated cell的apical H+ATPase, 也因為↓ENaC而使lumen電位較(+)而↓H+ secretion
- (主因)1.Hyperkalemia->p. tubules intracellular alkalosis->↓NH3產生(↓glutamine, glutamate deamination) and ↓bicarbonate reabsorption(核心本質為高血鉀引發之近端產銨障礙,集尿管排酸功能多保留且尿 pH 常可 <5.3;治療首要為「降血鉀」,血鉀正常化後產銨能力與酸中毒常隨之改善)
- For non-AG metabolic acidosis mechanism
- 多no Na wasting(因為angiotensin II and norepinephrine↑, 刺激proximal tubules再吸收Na)
- 所以isolated hypoaldosteronism很少見hyponatremiahyponatremia, 除非同時有cortisol deficiency(-->ADH↑), 所以hyponatremia要懷疑primary adrenal insufficiency
- Causing non-AG metabolic acidosis and hyperkalemia
2.Causes#
本節與Hyperkalemia之病因段落為同一套內容(該檔為主檔, 內容更完整); 此處僅留速查版。
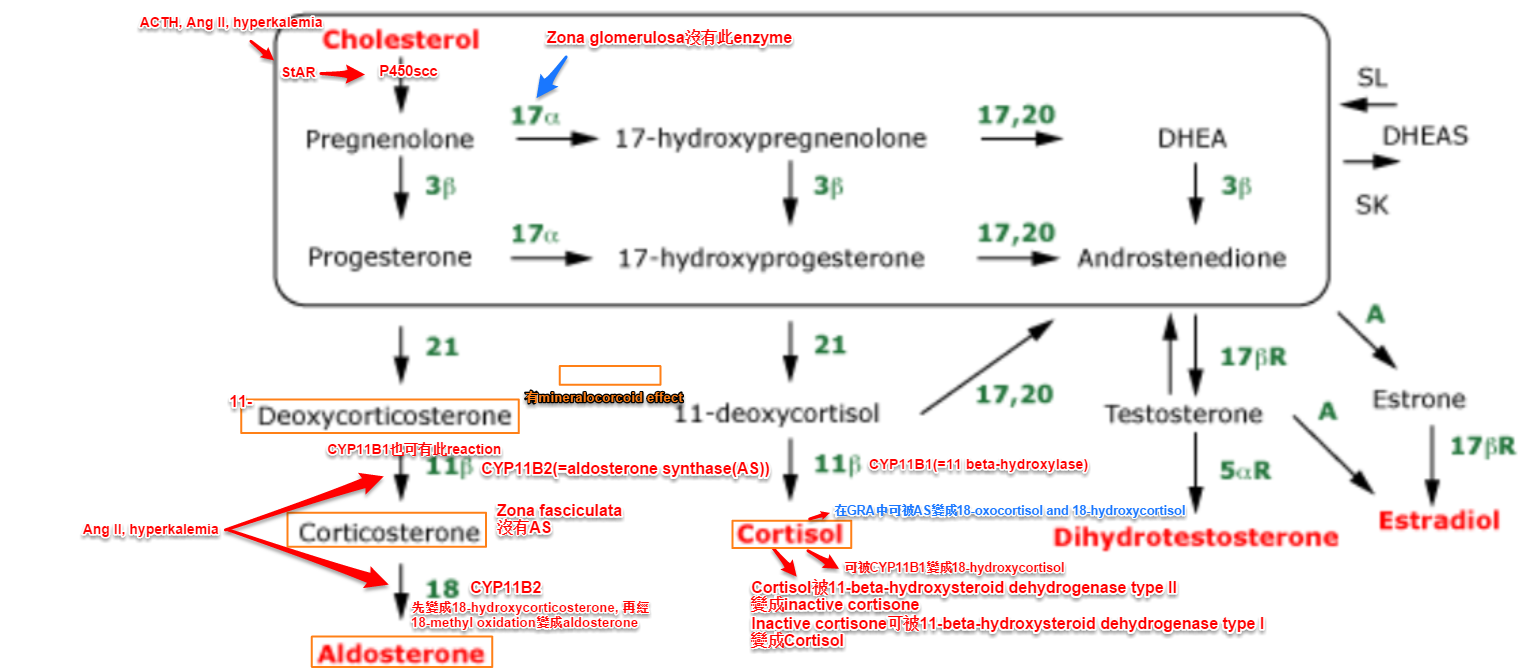
- Aldosterone resistance↑(aldosterone多↑, 除非IN傷到juxtaglomerular apparatus)
- K-sparing drugs: Trimethoprim/Pentamidine、Amiloride、Triamterene、Nafamostat(↓CAP→ENaC activity↓)、Spironolactone、Eplerenone
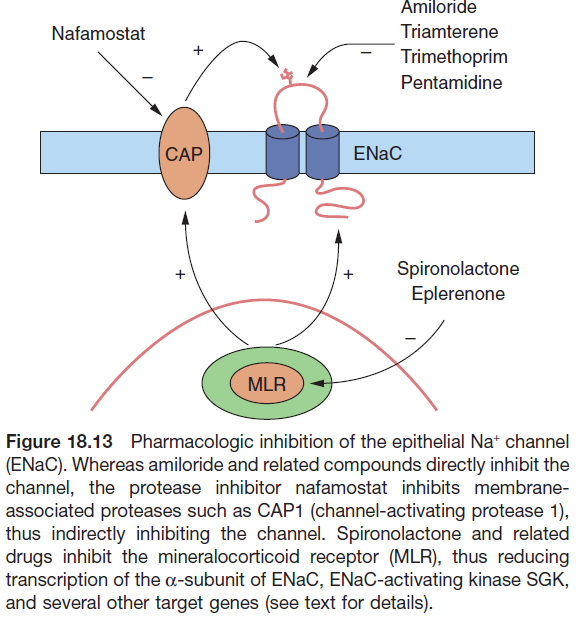 (Nafamostat 抑制 ENaC proteolytic cleavage 機轉圖)
- Principal cells 有問題: 會 CTIN 者皆可能(obstructive uropathy、chronic PN、SLE、移植後、HIV、amyloidosis、DM(另有 prorenin→renin defect)、lithium、medullary sponge kidney、sickle cell nephropathy); PHA type 1(AD=MR mutation 僅腎臟受影響; AR=ENaC mutation 全身性)、ureterojejunostomy(K 被 jejunum 再吸收)
- K-sparing drugs: Trimethoprim/Pentamidine、Amiloride、Triamterene、Nafamostat(↓CAP→ENaC activity↓)、Spironolactone、Eplerenone
- Aldosterone↓
- Renin normal~↓(hyporeninemic hypoaldosteronism; 典型 50-70 歲 DM nephropathy 或 CKD+CTIN): severe illness、AGN/CIN、DM(renin defect+volume expansion+autonomic dysfunction)、CNI/NSAID/beta-blocker、Gordon's syndrome(PHA2, WNK1/WNK4/CUL3/KLHL3; thiazide+限鹽可治)
- Renin↑: Addison's/primary adrenal insufficiency(TB/HIV/autoimmune/hemorrhage...)、heparin/ACEI/ARB、CAH(lipoid CAH、P450c21 缺乏)、congenital isolated hypoaldosteronism(P450c11AS)
3.Approaching#
- Renal echo, HIV, ANA, U/A, IgG/A/M, IFE, Cre, BUN, ACTH/cortisol, renin/aldosterone, Drugs review, one touch, HbA1C, FH
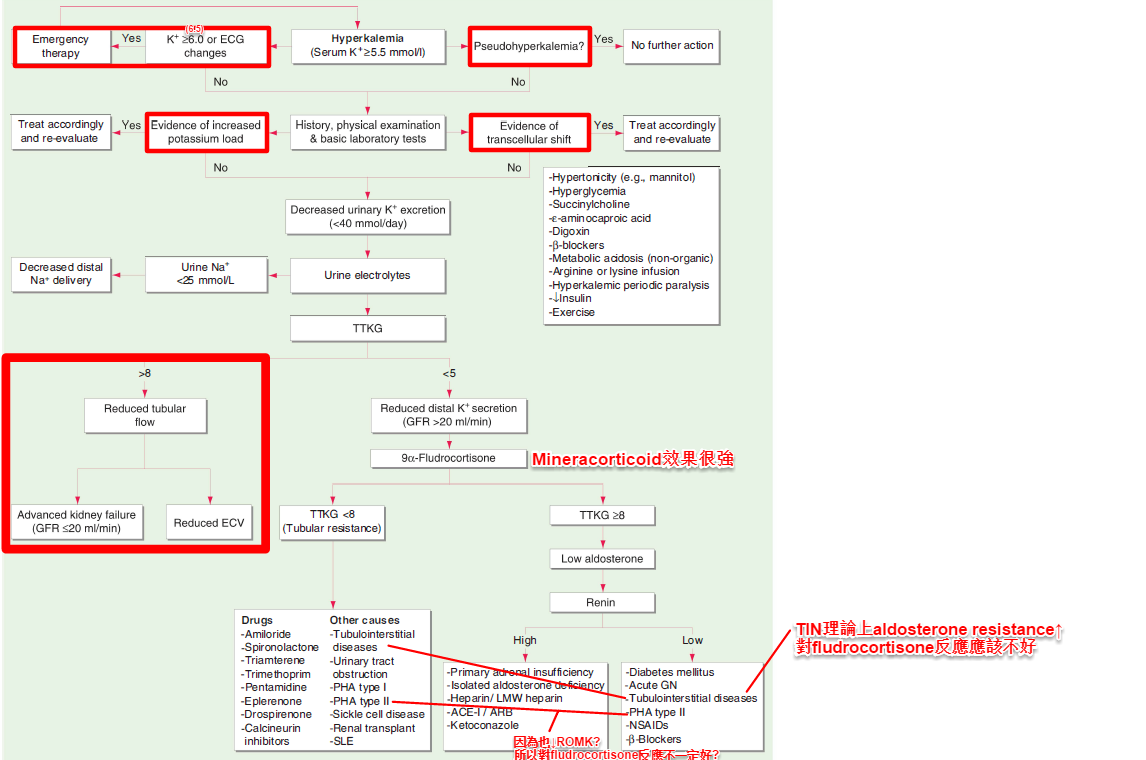
- 可以給fludrocortisone (0.1mg), then check TTKG 4hrs later, 若TTKG變成 >6(8)表示mineralocorticoid deficiency, but not resistance, is causative
- 註:TTKG 已被認為不可靠而不再建議常規使用(見Summary of electrolyte imbalance(also normal FeX and GI secretion concentration)); 本段保留為舊法/歷史考點, 現行改以 renin/aldosterone 對輸液與 fludrocortisone 之反應判讀
- 見下圖(hyperkalemia的approach流程圖)右下角
4.Tx#
- Tx of underlying
- Primary adrenal insufficiency
- Fludrocortisone 0.05-0.2mg/d
- Cortisone use
- Hyporeninemic hypoaldosteronism
- Fludrocortisone 0.2-1mg/d(較高, 因為大多也有一些aldosterone resistance)
- 不過這些病人常常有HTN, edema而不能用Fludrocortisone(因此常只用supportive care如Loop/thiazide diuretics and low K diet)
- 註:0.3mg的fludrocortisone會有1mg的prednisone的glucocorticoid effects
- 2020s更新: 高鉀處理可用patiromer(OPAL-HK, NEJM 2015; PMID 25415805:平均降鉀約 1.0 mmol/L)或sodium zirconium cyclosilicate(SZC/Lokelma)(HARMONIZE, JAMA 2014; PMID 25402495:48h內 98% 血鉀恢復正常)→讓RAASi/MRA得以續用;finerenone(non-steroidal MRA)於T2DM+CKD降腎與心血管結局風險(FIDELIO-DKD, NEJM 2020; PMID 33264825:hyperkalemia 停藥 2.3% vs 0.9%)〔PMID 25415805〕〔PMID 25402495〕〔PMID 33264825〕
- Fludrocortisone 0.2-1mg/d(較高, 因為大多也有一些aldosterone resistance)
- Primary adrenal insufficiency
- Supportive care
- 控制fluid status
- 治療hyperkalemia可↓metabolic acidosis, 因為NH3 excretion↑
- 考慮diuretics(loop, thiazide...看情況), laxatives, soda...
- Voltage defect者可考慮給Na+non-resorbable anion, 讓non-resorbable anion在CCD lumen中↑K+, H+ excretion; 所以可以給很多Soda with Acetazolamide(小心不要給太少soda而使Azol effect太強反而↑metabolic acidosis)