Alport syndrome/TBMD
1.Alport syndrome(hereditary nephritis)#
-
Epidemiology
- 3% child ESRD and 0.2% adults ESRD(U.S.)
- 1/50000 newborn
-
Genetic and pathogenesis
- 和mutation of encoding type IV collagen中α3, α4, α5的gene有關(normally located in kidney(glomerulus(α3, α4, α5), Bowman's capsule(α3, α4, α5)(α5, α5, α6), distal tubules(α3, α4, α5), cochlea(α3, α4, α5), eye basement membrane(α3, α4, α5))
- 共有6種α chains(1-6), 形成(1,1,2)(BMs and embryonic GBM); (3,4,5)(adult GBM); (5,5,6)(Bowman's capsule), 缺其中一個會形成不了trimer
- 所以也有sensorineural hearing loss, ocular abnormalities
- Skin表皮基底膜只有α1, α2, α5, α6(無α3, α4), 所以skin biopsy只能染α5來診斷X-linked Alport(男缺失, 女mosaic), 無法診斷AD/AR Alport或TBMD
- 多X-linked(COL4A5 gene=>α5)(所以♀也可有, 因為X-inactivation, 但表現就variable); 可AR(~15%)(COL4A3 or COL4A4雙對偶基因突變), AD(傳統教科書~5%, 但近年成人NGS世代發現COL4A3/A4雜合變異可占20-30%)(COL4A3 or COL4A4), 有些家族甚至多基因遺傳; 家人也會洗腎; 異合子COL4A3/A4即屬AD Alport光譜,舊稱TBMD/benign familial hematuria已改歸此類而非必然良性〔PMID 33094278〕
- Jais等(JASN 2000; PMID 10752524):XL男性基因型預後相關,大片段缺失/無義突變(nonsense)/移碼突變者30歲前ESRD機率達90%,顯著高於錯義突變(missense,50%)〔PMID 10752524〕
- X-linked和AR表現類似, 多16-35y/o ESRD
- AD則損失renal function較慢(多45-60y/o ESRD) ; AD之deafness/ocular abnormalities較X-linked/AR罕見且較晚發(非絕對沒有)
- 和mutation of encoding type IV collagen中α3, α4, α5的gene有關(normally located in kidney(glomerulus(α3, α4, α5), Bowman's capsule(α3, α4, α5)(α5, α5, α6), distal tubules(α3, α4, α5), cochlea(α3, α4, α5), eye basement membrane(α3, α4, α5))
-
S/S
- Kidney
- 多asymptomatic microscopic hematuria since early childhood(可有dysmorphic RBC and RBC casts); then recurrent episodes of gross hematuria(often after URI(所以D/D MPGN, PSGN, IgAN...)); 若♂到了10 y/o仍無hematuria則不太像Alport syndrome
- 會progressive proteinuria(even可nephrotic syndrome(FSGS?, EM 的確可以看到一些podocyte effacements; 也有說法是basement membrane和podocytes attachment/survival有關, 所以會影響podocytes而FSGS))
- 一般anti-GBM disease是anti-α3 NC1 domain Ab, 但Alport's syndrome者因為α5有問題會連帶使α3無法正常組成GBM, 所以不常產生anti-α3 NC1 domain Ab
- Cochlea
- the rate of hearing loss和CKD progression速度類似
- Brenner(p1443):High-frequency sensorineural deafness occurs in 30% to 50% of patients. Hearing impairment is always accompanied by renal involvement. The severity of hearing loss is variable, and there is no relation between the severity of hearing loss and of the renal disease
- ♂ 85% 15y/o以前有detected hearing impairment
- Eye(15-30%)
- Cornea
- Recurrent erosions, posterior polymorphous dystrophy
- Lens
-
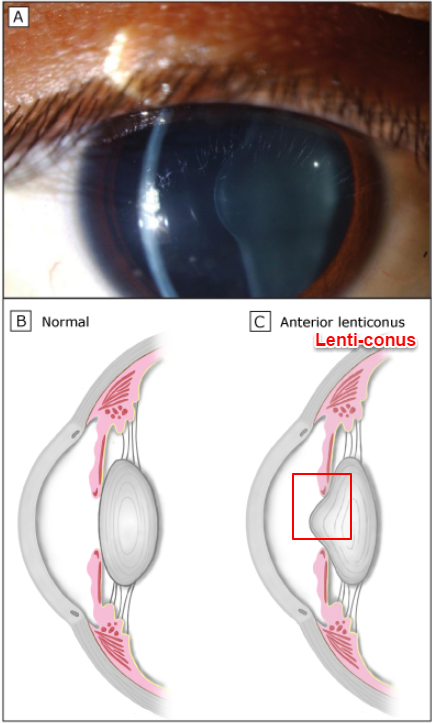
Anterior lenticonus(due to thinning of the lens capsule)
- 20-30% male X linked Alport syndrome and is pathognomonic
- 也with subcapsular cataracts
-
- Cornea
- Kidney
-
Retina
- Bilateral white or yellow granulations that are superficially located in the retina surrounding the foveal area(specific to Alport syndrome)
- 多asymptomatic but可導致macular holes with impaired vision
- Bilateral white or yellow granulations that are superficially located in the retina surrounding the foveal area(specific to Alport syndrome)
-
Leiomyomatosis
-
2-5% X-linked Alport syndrome
-
Large vessel(aorta, intracranial...) aneurysm
-
Case reports
-
Diagnosis
- Confirm by renal biopsy or skin biopsy or genetic study
- Renal biopsy
- LM:可normal or mild mesangial proliferation or glomerulosclerosis(可FSGS) and IFTA
- IF:原則上是(-)
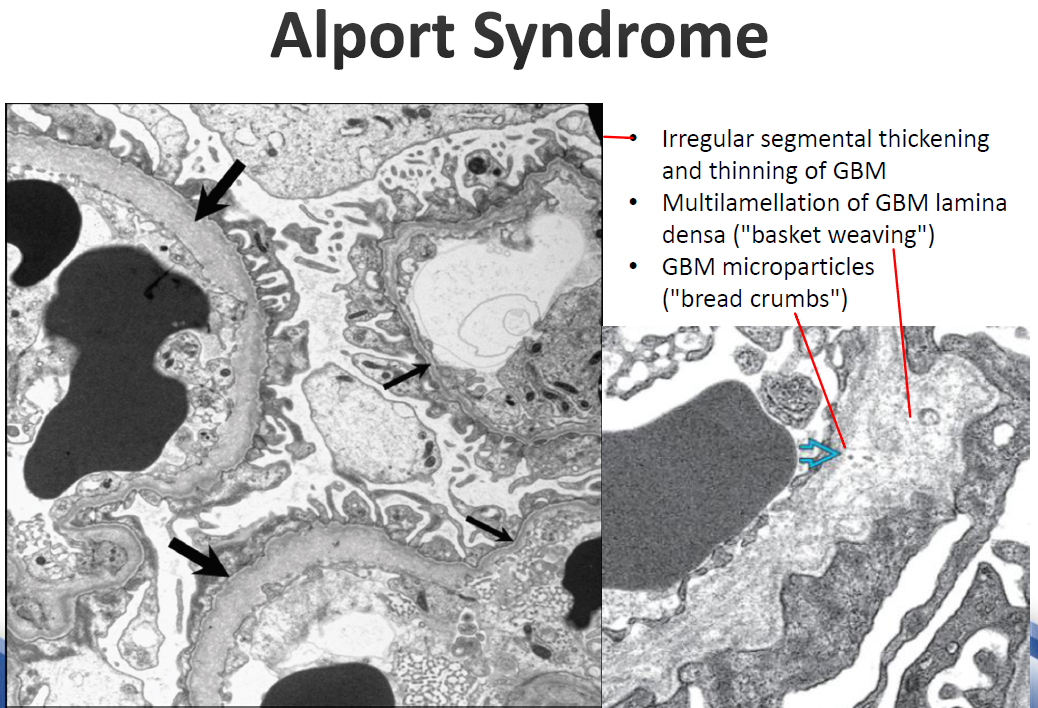
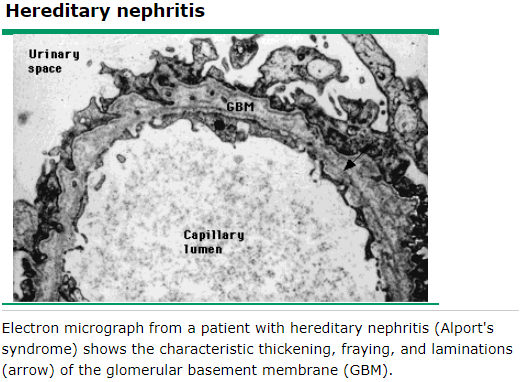
- EM:Irregular segmental thickening and thinning of GBM, multilamellation of GBM lamina densa("basket weaving"(籃網編織)), GBM microparticles("bread crumbs"(麵包屑)), +/- podocyte foot process effacement(所以前面說可有nephrotic syndrome/FSGS...)
- 不過早期(young Pts)可以no laminated GBM
- 30% by 10 y/o, 90% by 30 y/o
- 也可用immunostaining染α3, α4, α5 chains of type IV collagen
- 不過早期(young Pts)可以no laminated GBM
- Skin biopsy也是用immunostaining染α3, α4, α5 chains of type IV collagen(不過commercially available monoclonal antibody只有α5)
- Renal biopsy
- Confirm by renal biopsy or skin biopsy or genetic study
- 若by臨床則FH+CKD+sensorineural hearing loss +/- characteristic ocular findings
- D/D
- TBMD(FH of hematuria but no ESRD(其實未必?) nor deafness)
- MYH9(myosin heavy chain 9) related diseases(AD)
- 和non-muscle myosin有關; 內含4個syndromes(含Epstein syndrome...), 都有giant PLT, thrombocytopenia(會出血), neutrophil basophilic inclusion bodies, 其中某些人也有sensorineural hearing loss, cataract(但沒有anterior lenticonus); nephritis(影響mesangial cells and podocytes, 受影響者常<40 y/o ESRD)
- 也和黑人的CKD(MYH9 gene, Apo-L1 gene)有關
- IgAN, PSGN, MPGN...
- Tx
- Check UACR/UPCR Q1y
- if UPCR>0.2 or >4 mg/m2/hr
- Add ACEI/ARB to achieve UPCR<0.5 (decrease proteinuria and CKD progression)(1B)
- EARLY PRO-TECT (Kidney Int 2020; PMID 32299679): 兒童期確診 Alport 症候群於微量白蛋白尿期及早投予 ramipril 可顯著延緩進入 ESKD 達數十年〔PMID 32299679〕
- Kashtan & Gross(Pediatr Nephrol 2021; PMID 33159213):指引建議XL男性及AR男女確診時即起始ACEi治療;XL女性及AD男女則於微量白蛋白尿期即起始治療〔PMID 33159213〕
- SGLT2i: 蛋白尿性CKD支持治療(eGFR≥20+albuminuria,不論DM),Alport亦適用此原則〔PMID 32970396〕; 早期ACEI/ARB治療可延緩ESRD
- Add ACEI/ARB to achieve UPCR<0.5 (decrease proteinuria and CKD progression)(1B)
- if UPCR>0.2 or >4 mg/m2/hr
- Others as CKD care
- ENT transfer for hearing impairment
- If ESRD-->renal transplantation
- 雖然不會有recurrence of Alport syndrome, but 3% male X-linked Alport syndrome者會de novo產生anti-GBM Ab(大多移植後1年內發生, 多為失聰且<30 y/o的男性)(因為有之前身體未見過的antigen(new α5 chain NC1)出現, 大多產生的Ab辨認的Ag和一般的anti-GBM disease的Ag(一般anti-GBM disease Ab打的是α3 chain的NC1 domain)不一樣)-->crescent GN(=>Endoxan and Solumedrol)
- 註:Commercial kit of anti-GBM Ab主要是針對Goodpasture's disease, epitope會有點差異, 所以should not rely solely on commercial anti-GBM assays
- 雖然不會有recurrence of Alport syndrome, but 3% male X-linked Alport syndrome者會de novo產生anti-GBM Ab(大多移植後1年內發生, 多為失聰且<30 y/o的男性)(因為有之前身體未見過的antigen(new α5 chain NC1)出現, 大多產生的Ab辨認的Ag和一般的anti-GBM disease的Ag(一般anti-GBM disease Ab打的是α3 chain的NC1 domain)不一樣)-->crescent GN(=>Endoxan and Solumedrol)
- Check UACR/UPCR Q1y
2. 體染色體 Alport 症候群光譜 (Autosomal Alport Syndrome Spectrum / AD Alport, 舊稱 TBMD 或良性家族性血尿)#
- 國際專家共識與命名金句 (Kashtan JASN 2021; PMID 33094278):
- 正式建議廢除單純「良性家族性血尿 (benign familial hematuria, BFH)」名詞,將帶有 COL4A3 或 COL4A4 雜合變異 (heterozygous variants) 者歸類為 Autosomal Alport syndrome spectrum。
- 此類患者並非必然良性,一生中仍有相當比例隨年齡出現顯著蛋白尿、高血壓、次發性 FSGS 樣病變甚至進展至 CKD/ESKD;臨床應終生定期追蹤,若出現蛋白尿應及早投予 ACEi/ARB 與 SGLT2i 保護。
- Epidemiology
- 5-10% in general population but <1% diagnosed
- Genetic and pathogenesis
- 多為heterozygous defects in COL4A3 or COL4A4
- =carrier of AR form Alport syndrome ==>AD Alport 光譜,預後不一定良性,合併proteinuria/CKD/FSGS者需嚴格追蹤〔PMID 33094278〕
- 所以其實和典型 Alport 症候群屬於同一疾病光譜 (spectrum disease),預後不宜一概視為良性
- 不過也有一些人是一些未知的genetic change not COL4A3 or COL4A4
- 30-50%有FH of hematuria
- 多為heterozygous defects in COL4A3 or COL4A4
- S/S
- 多persistent asymptomatic microscopic hematuria due to transient ruptures in the glomerular capillary wall
- 所以可有dysmorphic RBC and RBC casts
- 可episodes of gross hematuria after URI(like IgA nephropathy or PSGN...)
- 可腰痛with gross hematuria, 研究顯示40% TBMD Pts有hypercalciuria and/or hyperuricosuria(why?), 所以hematuria和stone有關(?)
- 可因為glomerular hematuria而ATN(RBC casts塞住; RBC lysed而放出iron導致free radicals)
- 有些人會有proteinuria(but 多<1.5g/d) and hypertension
- 和Alport's syndrome不同, rare nephrotic range proteinuria
- 可伴隨FSGS而slowly progressive deterioration of renal function
- 多persistent asymptomatic microscopic hematuria due to transient ruptures in the glomerular capillary wall
- Diagnosis
- Glomerular hematuria with FH of hematuria but no ESRD(其實未必); no CKD(其實未必), no proteinuria(其實未必, 因為basement membrane和podocyte attachment/survival有關, 所以會有secondary FSGS)
- 多不用renal biopsy(but consider renal biopsy if sporadic case or FH of ESRD or proteinuria(+))
- Renal pathology
- LM:可normal or mild mesangial proliferation
- EM
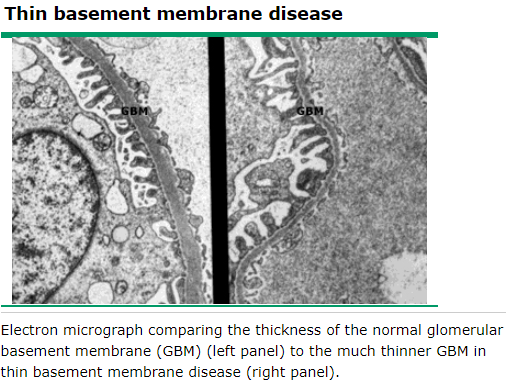
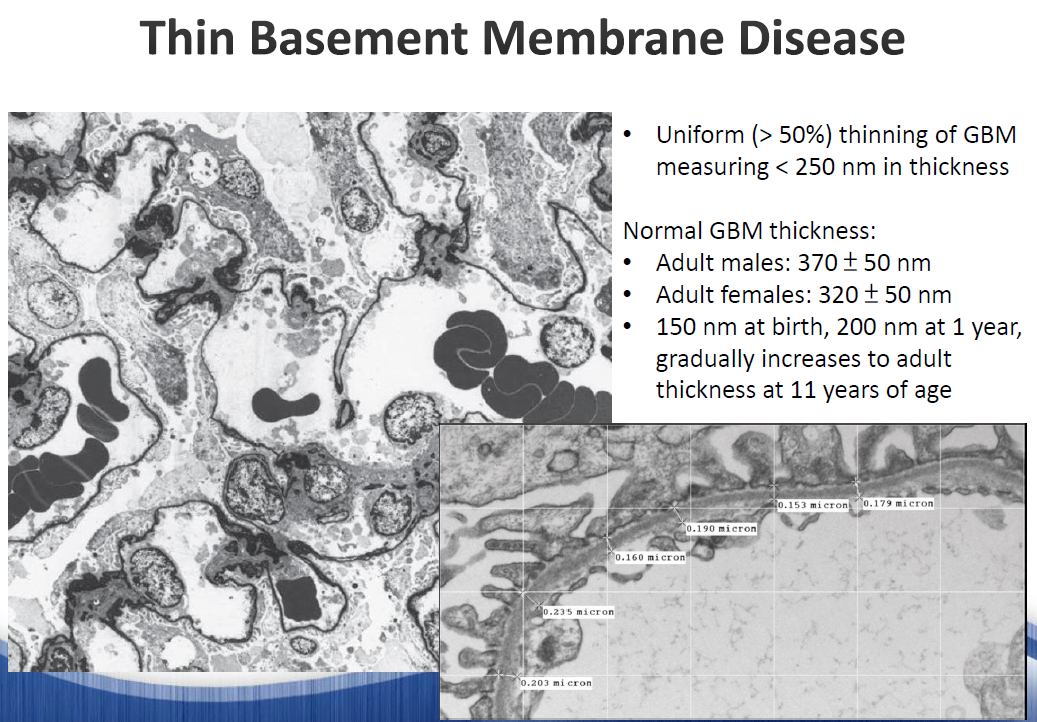
- Uniform (>50%) thinning of GBM [Adult <200-250nm; child(2-11 y/o) <180-250nm]
- Renal pathology
- D/D
- IgAN, PSGN, MPGN...
- Alport syndrome
- Alport syndrome多X-linked, TBMD多AD
- TBMD no hearing impairment nor ocular abnormalities nor ESRD(其實未必)
- 可染alpha-5(IV) chain來輔助診斷(??, 不是COL4A3 和 COL4A4 嗎?)
- Genetic test
- Tx
- Add ACEI/ARB to achieve UPCR<0.5 (2B)
- Treating hypercalciuria or hyperuricosuria 可decrease hematuria?