Amyloidosis and MIDD
Data from uptodate
- Overview of amyloidosis
- Renal amyloidosis
- Clinical presentation, laboratory manifestations, and diagnosis of immunoglobulin light chain (AL) amyloidosis
- Pathogenesis of immunoglobulin light chain (AL) amyloidosis and light and heavy chain deposition diseases
- Treatment and prognosis of immunoglobulin light chain (AL) amyloidosis and light and heavy chain deposition diseases-summary only
- Causes and diagnosis of AA amyloidosis and relation to rheumatic diseases
- Treatment of AA (secondary) amyloidosis
- Dialysis-related amyloidosis
(也見-CKD/AKI/ACKD evaluation-MM(multiple myeloma) related renal disease)
1.Mechanism#
- LMW proteins(5-25kDa)因為各種原因conformational change(antiparallel beta-pleated sheet configuration) +/- other non-fibrillar substances(GAG, serum amyloid P(SAP; 所以SAP可用來做scintigraphy), apolipoproteins E and J...)-->amyloid fibrils depositions-->apple-green birefringence under polarized light and thioflavine T with intense yellow-green fluorescence
2.Pathology#
- LM
Light micrograph showing glomerular amyloidosis
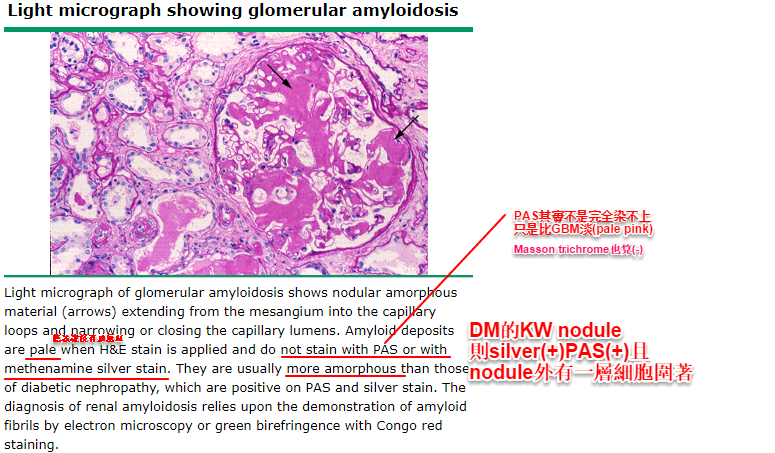
- 註:Masson trichrome stain amyloidosis是灰藍色的, MIDD是淡紅色的(→ 見下方MIDD病理段)
- Poor correlation between the extent of glomerular amyloid deposits and the degree of proteinuria
- 因為主要是mesangium堆積?
- 早期amyloidosis LM可完全正常, IF若非AL nor AH也會(-), 此時只能用congo red, EM(fibrils)診斷
Amyloidosis, Early Stage
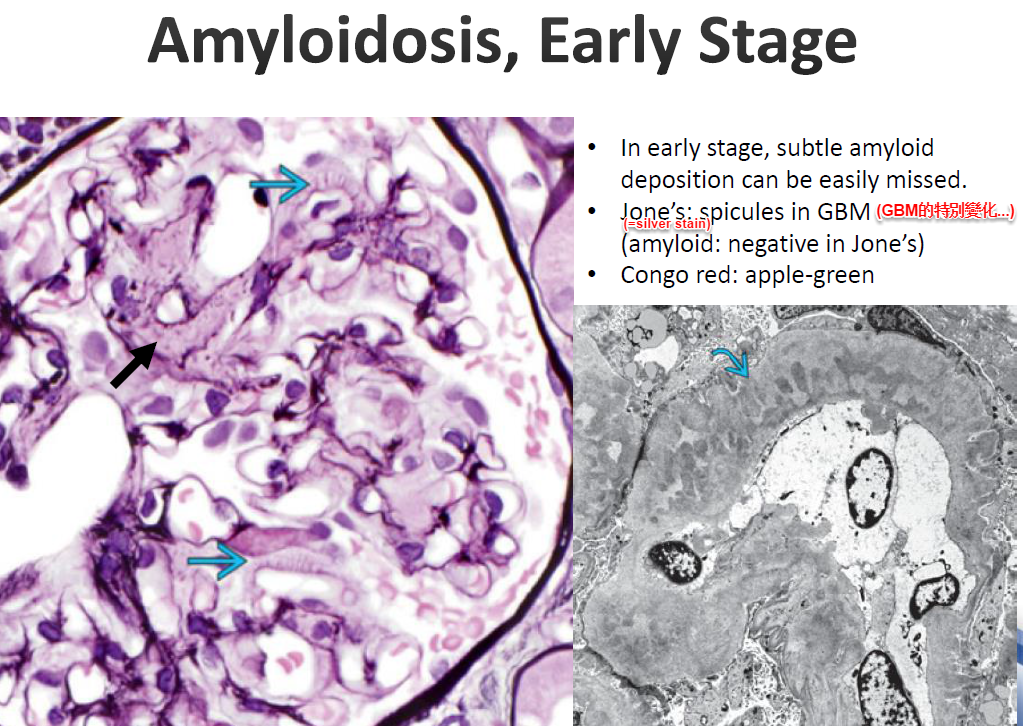
- In early stage, subtle amyloid deposition can be easily missed.
- Note "spicules in GBM (amyloid- negative in Jones)"
- Congo red: apple-green
Amyloidosis
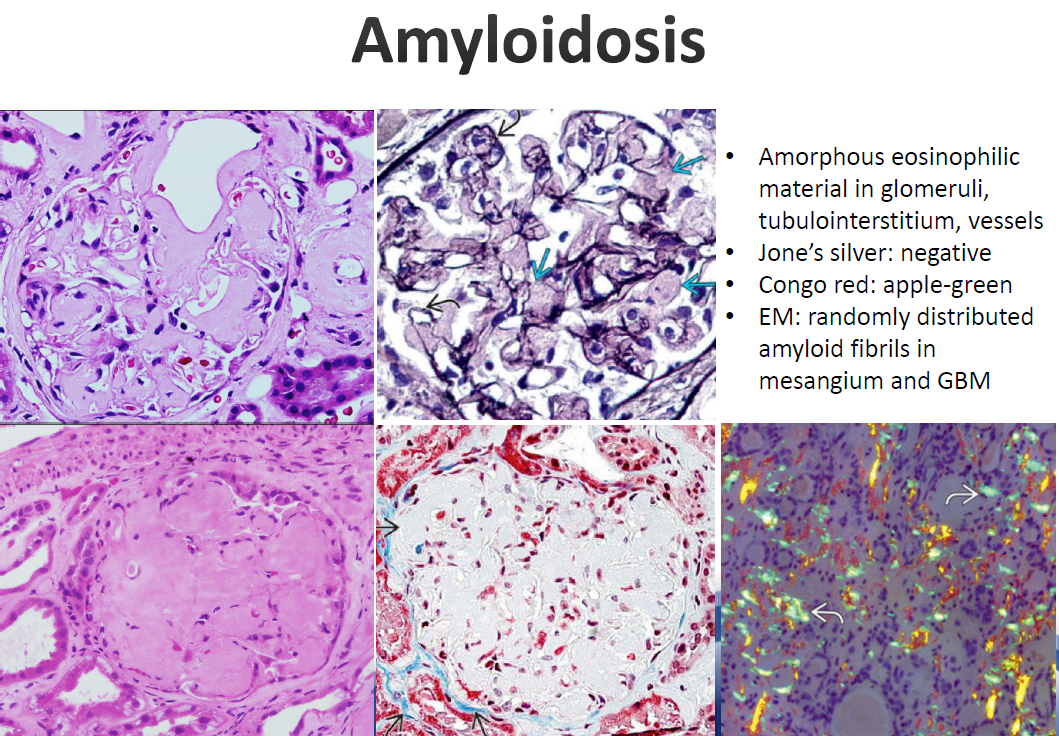
- Amorphous eosinophilic material in glomeruli, tubulointerstitium, vessels
- Jones's silver: negative
- Congo red: apple-green
- EM: randomly distributed amyloid fibrils in mesangium and GBM
Vascular renal amyloidosis
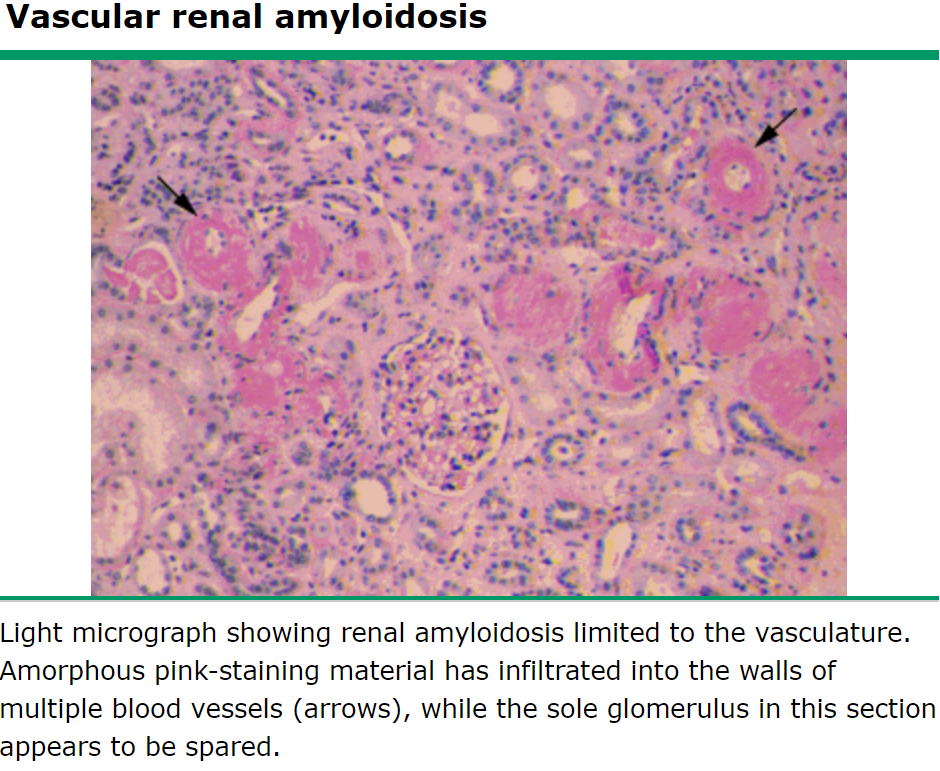
- Light micrograph showing renal amyloidosis limited to the vasculature. Amorphous pink-staining material has infiltrated into the walls of multiple blood vessels (arrows), while the sole glomerulus in this section appears to be spared.
- (Uncommon)
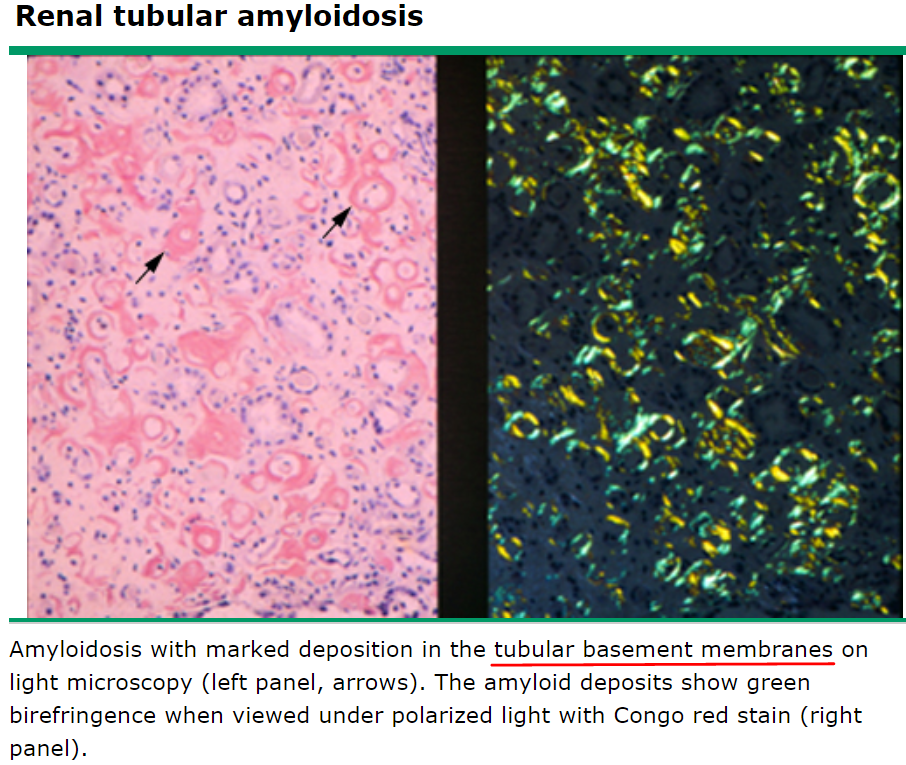
Renal tubular amyloidosis
-
Amyloidosis with marked deposition in the tubular basement membranes on light microscopy (left panel, arrows). The amyloid deposits show green birefringence when viewed under polarized light with Congo red stain (right panel).
-
(Uncommon)
-
Congo red
Congo red stain in amyloidosis
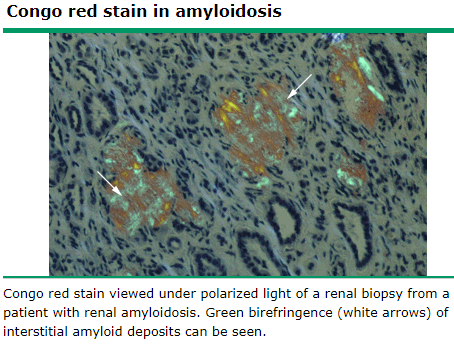
- Congo red stain viewed under polarized light of a renal biopsy from a patient with renal amyloidosis. Green birefringence (white arrows) of interstitial amyloid deposits can be seen.
- Sensitivity:57-85%, specificity:92-100%
- 小心very early amyloidosis or AH amyloidosis可以congo red(-)!!
- Immunofluorescence
- Negative for Ig and complement in AA but is typically (+) for κ or λ(monoclonal) light chains in AL
- EM
Electron micrograph showing renal amyloidosis
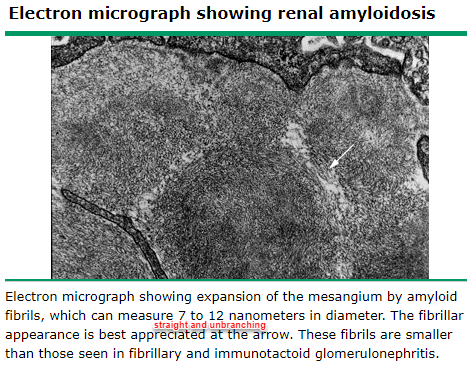
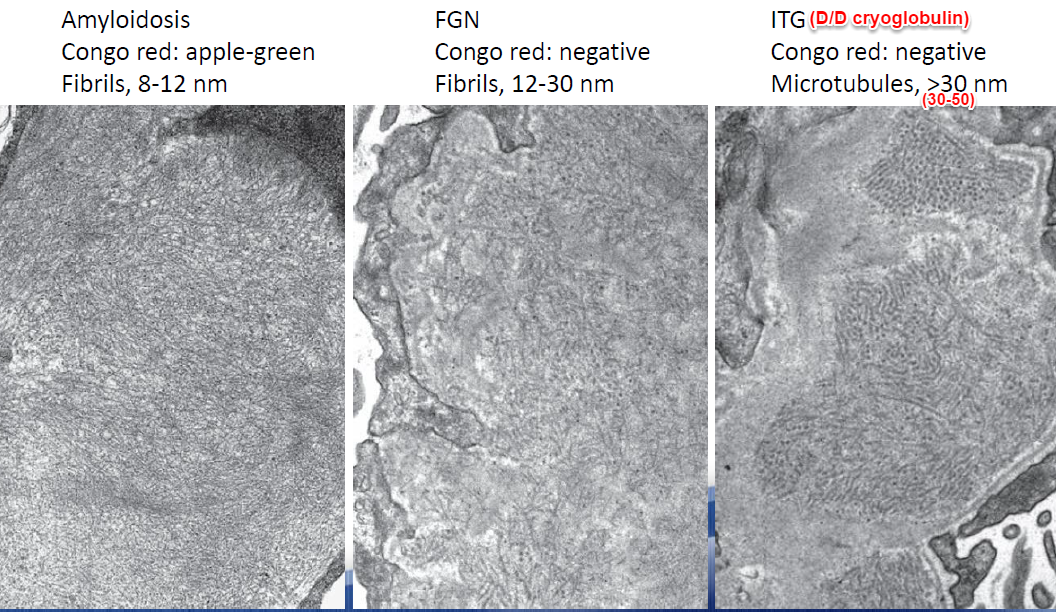
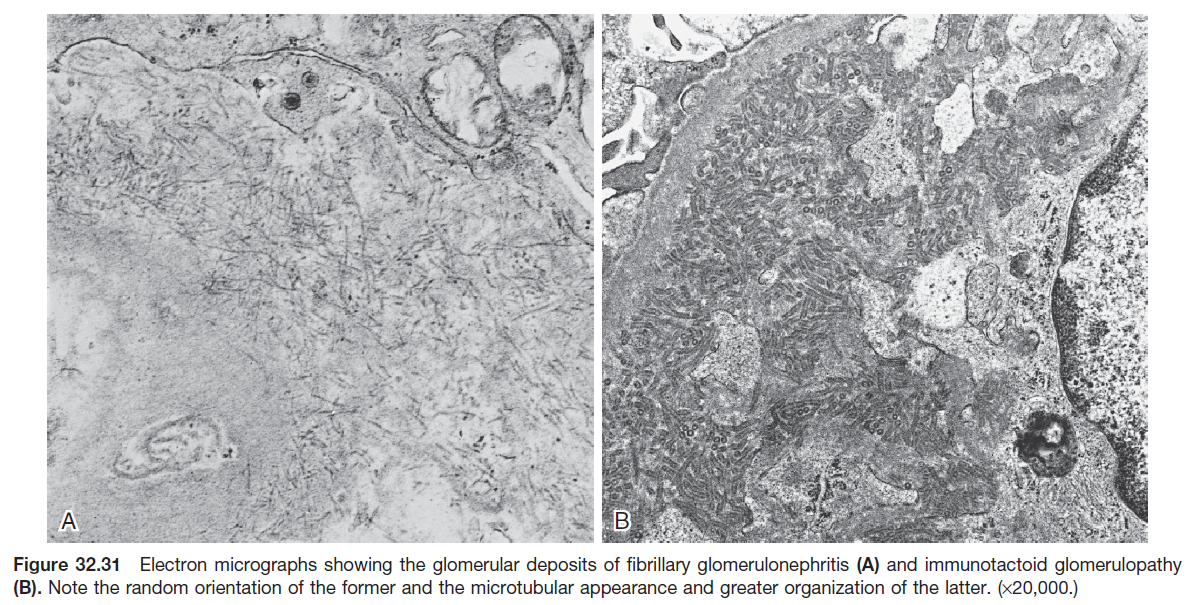
- Electron micrograph showing expansion of the mesangium by amyloid fibrils, which can measure 7 to 12 nanometers in diameter. The fibrillar appearance is best appreciated at the arrow. These fibrils are smaller than those in fibrillary and immunotactoid glomerulonephritis.
- Randomly distributed fibrillar(7-12 nm) deposits in the mesangium/GBM
- D/D
3.Types#
- AH(rare)
- Ig heavy chains deposition
- S/S and course和AL類似
- AL
- Incidence:1/10W/yr, 多發生在>40 y/o, 65-70%為♂
- Ig light chains from plasma cells dyscrasias
- 多為λ chains(70%) fragments(from macrophage代謝後的light chains殘渣; 所以不常伴隨cast nephropathy(但少數個案仍可以有), 因為Tubular damage and tubular obstruction in myeloma kidney require the filtration of "intact" light chains), variable area(所以染色不一定, 所以堆積在哪不一定); κ chains(25%); biclonal(5%)
- Uptodate:In AL amyloidosis, λ light chains may be more amyloidogenic than κ light chains
- Monoclonal:IgG: 35%, IgA: 10%, IgM: 5%, IgD: 1%, and light chains in the remaining Pts
- 【必考病理鑑別】AL Amyloidosis vs. LCDD (MIDD) 核心速查對比(Brenner 11e Ch 29/30):
- AL Amyloidosis:
- 輕鏈類型: 以 λ 輕鏈 為主 (~70%),常為巨噬細胞代謝後之片段 (fragments)
- 超微結構 (EM): 隨機排列、無分支之實心微纖維 (fibrils, 直徑 7–12 nm)
- 特殊染色: Congo red (+),偏光顯微鏡下呈典型蘋果綠雙折光 (apple-green birefringence)
- 器官受累: 心臟極常受累 (~60%)(限制型心肌病變、傳導障礙);診斷時平均 Cre 較低 (~1.1 mg/dL)
- LCDD (Light Chain Deposition Disease):
- 輕鏈類型: 以 κ 輕鏈 為主 (~70%)
- 超微結構 (EM): 非纖維狀、點狀粉末狀 (powdery) 電子緻密沉積
- 特殊染色: Congo red (-),Thioflavine-T (-)
- 器官受累: 極顯著侵犯 TBM (腎小管基底膜) 與 Bowman's capsule;極少侵犯心臟;診斷時常已有嚴重腎功能不全 (Cre 常 >4.0 mg/dL)
- Monoclonal immunoglobulin deposition disease (MIDD, 含HCDD, LCDD, LHCDD; LCDD佔了80%)
- MIDD大多還是from MM(LCDD or LHCDD都約50%有MM, HCDD約25%有MM), 不過也可from WM, CLL, nodal marginal zone lymphoma or chronic infection or autoimmune
- LCDD多nephrotic syndrome, 多progressed to ESRD(因為還常involve tubular BM, 所以不只glomerulus出問題, tubules也會出問題); 可involve liver, GI; rarely involve heart
- LCDD often associated with deposits in the TBM and Bowman's capsule(vs. AL)
- 註:回思pathology:MIDD在TBM的沉積比amyloidosis嚴重~
- LHCDD/HCDD(rare)
- Produces both light and heavy monoclonal immunoglobulin chains or only short (truncated) heavy chains
- S/S and course和LCDD類似
- Pathology
- LM
- 類似amyloidosis but 可以MPGN pattern; H-E stain and PAS會比amyloidosis紅一些, silver stain(-), congo red(-), Masson trichrome stain是淡紅色的(amyloidosis是灰藍色的)
- Immunofluorescence
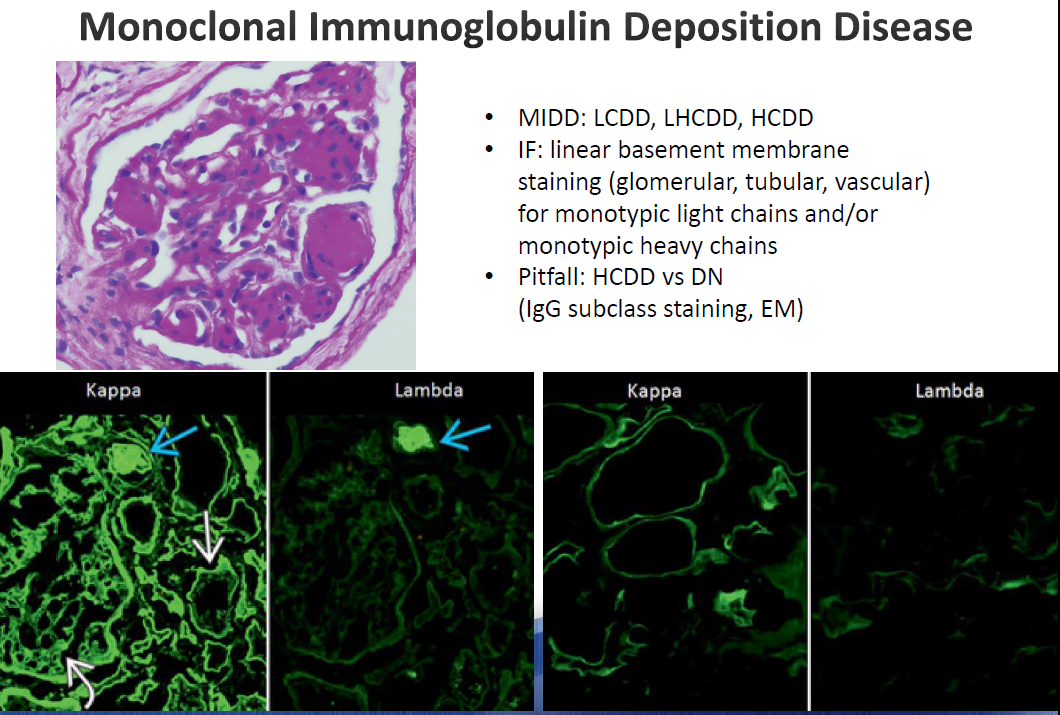
- Linear BM(glomerular, tubular, vascular) for monotypic light chains and/or monotypic heavy chains
- HCDD(IgG)需要和DM nephropathy D/D
- 用(IgG subclass staining, EM)來分
- Linear BM(glomerular, tubular, vascular) for monotypic light chains and/or monotypic heavy chains
- LM
- AL Amyloidosis:
- EM
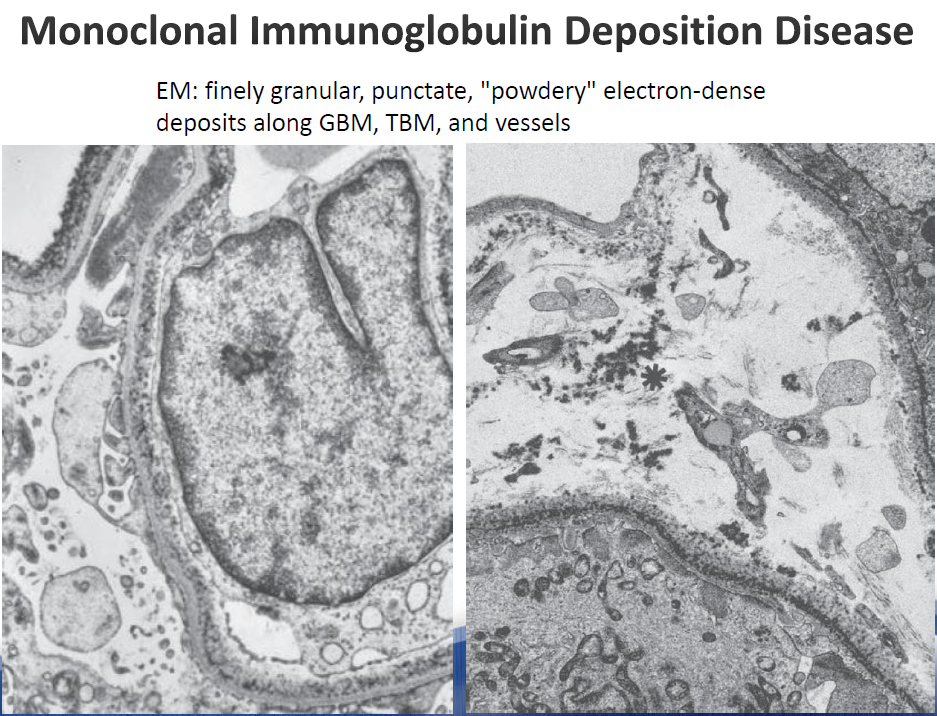
- Finely granular, punctate, "powdery" electron dense deposits along GBM, TBM, and vessels
Monoclonal Immunoglobulin Deposition Disease
- 可with MM, P(PNS, ANS)OE(pituitary, thyroid, adrenal↓)MS, WM(註:IgM-associated AL amyloidosis, 較少cardiac involvement), lymphoplasmacytic lymphoma, NHL, CLL
- 值得一提的是, 大多MM沒amyloidosis, 而大多amyloidosis沒MM, 所以有一些其他因素
- 1.不是所有light chains都可形成fibrils
- 2.macrophage代謝light chains後的fragments要能形成amyloid fibrils
- 3.(Renal amyloidosis)mesangial cells要會uptake light chains by endocytosis
- 4.Other factors influence fibril formations...
- 若AL有MM, 大多一起被診斷或MM診斷在AL之前, 少數MM診斷在AL之後
- 所以不一定MM, AL誰先出來
- S/S
- Heart(60%)(不過IgM-associated AL amyloidosis, 較少cardiac involvement; MIDD也少involve heart)
- Restrictive cardiomyopathy, conduction blockage, arrhythmia, ACS(coronary arterial depositions)
- Hepatomegaly(22%?) +/- splenomegaly (70%)
- Cholestasis pattern with elevated liver enzymes(25%) (=infiltrative type?)
- GI(不常見, clinically apparent僅1%)
- Bleeding(due to vascular fragility and loss of vasomotor responses to injury)
- Autonomic dysfunction
- Lung(tracheobronchial infiltration, lung nodules, pleural effusions, (rare)pulmonary HTN)
- Nephro
- 75% proteinuria
- 50%Nephrotic syndrome
- Nephrotic syndrome者20% ESRD
- 也可以只deposit在(BV) or (tubules basement membranes)而no obvious proteinuria but ESRD
- 可Type I, II RTA, NDI
- (Rare)可intratubular casts formation similar to light chain cast nephropathy
- Bleeding(factor X deficiency due to binding to amyloid fibrils primarily in the liver and spleen; liver dysfunction; acquired vWF disease; BV depositions), purpura(尤其raccoon eyes(specific to AL))
- Musculoskeletal problems(可enlarged muscles(pseudohypertrophy), arthropathy(可和dialysis related amyloidosis一樣involve shoulder joint...))
- Waxy skin, subcutaneous nodules or plaques
- Carpal tunnel syndrome(需screen amyloidosis), peripheral neuropathy(motor+sensory)(20%), CNS neuropathy, autonomic dysfunction(15%)
- 所以CNS, PNS, ANS都可involved
- Macroglossia
- Others:
- BWL, fatigue...
- Heart(60%)(不過IgM-associated AL amyloidosis, 較少cardiac involvement; MIDD也少involve heart)
- Tx
- 先做risk-stratify(Mayo cardiac staging:NT-proBNP/troponin/dFLC)決定治療強度與SCT適格性; 治療目標是hematologic response(↓involved FLC、dFLC, 目標≥VGPR/CR)→才會有organ response
- 一線標準首選: Dara-CyBorD (daratumumab + bortezomib + cyclophosphamide + dexamethasone)
- ANDROMEDA (NEJM 2021; PMID 34192431): Daratumumab 聯合 CyBorD 使初診 AL 澱粉樣變性患者血液學完全緩解率 (CR) 顯著提高近三倍 (53.3% vs 18.1%),且顯著延長器官無惡化存活期,確立為當代第一線標準治療〔PMID 34192431〕
- Bortezomib(Velcade)-based(CyBorD/VCd)為backbone; 不適合dara者仍可用
- Autologous SCT(PBSCT):僅適用體能佳、low cardiac stage、dFLC不過高者(約僅20%符合); 高stage者SCT風險高
- Supportive:心/腎(ACEI/ARB小心低血壓)/利尿; 注意factor X deficiency與acquired vWF所致出血
- 新興:anti-fibril Ab(birtamimab、CAEL-101)、venetoclax(t(11;14))等試驗中
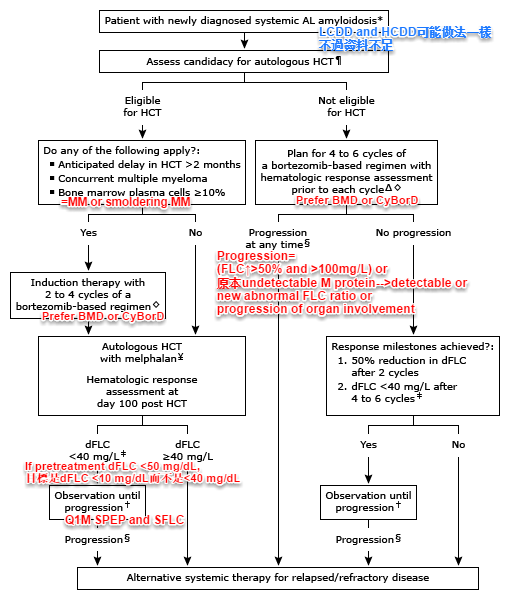
Patient with newly diagnosed systemic AL amyloidosis算一些
-
dFLC: difference between involved and uninvolved serum FLC levels
- 即「受侵犯之單株輕鏈濃度 − 未受侵犯之多株輕鏈濃度」(mg/L); 用於 Mayo 分期與血液學反應評估, 治療後 dFLC <10 mg/L 或下降 >90% 為極佳反應(VGPR/CR)
-
Renal transplantation could be considered if hematologic complete remission
-
Predictors of renal response
- Baseline low Cre and lower proteinuria
- Hematologic response(+), serum free light chains level↓↓↓(3M內↓>90%)
- 不過amyloidosis, MIDD renal function常常non-reversible, 會慢慢進展成ESRD
-
AA
- From SAA被macrophage degradation後的碎片(serum amyloid A; acute phase proteins produced by liver(if 受IL-1刺激))
- Etiologies
- I
- TB(amyloidosis(AA), also MCD, collapsing FSGS, IgAN), leprosy, COPD, cystic fibrosis, subacute IE, osteomyelitis, chronic pyelonephritis, skin ulcers
- Whipple's disease
- HBV(?)
- I(60%)
- RA(常>15yrs), IBD/sero (-) spondyloarthropathy, FMF(familial Mediterranean fever), AOSD, SLE(rare, 原因未知, 不過SAA level抽起來確實比RA低), vasculitis(Giant cell arteritis, Takayasu arteritis, Behcet's diseases, PAN), IgG-4 related diseases
- RA以前常有glomerular AA depositions and 常常ESRD
- 隨著治療進步,現在不常見, 因為大多發生在poor controlled, seropositive, long-standing and 有extraarticular manifestation的RA
- RA可crescent GN(uncommon), 可能因為RA本身造成的GN or amyloid fibril-induced ruptures in the capillary loops
- 其他AL, AA也可以crescent GN但是很少見
- RA以前常有glomerular AA depositions and 常常ESRD
- RA(常>15yrs), IBD/sero (-) spondyloarthropathy, FMF(familial Mediterranean fever), AOSD, SLE(rare, 原因未知, 不過SAA level抽起來確實比RA低), vasculitis(Giant cell arteritis, Takayasu arteritis, Behcet's diseases, PAN), IgG-4 related diseases
- M
- 尤其HL, RCC
- 可Hairy cell leukemia, castleman disease
- 可Lung/GI/GU adenocarcinoma, hepatic adenoma, BCC
- Others
- Drugs abuser(感染相關?)
- Gout(case report)
- I
- S/S
- Heart as above(10%, 比AL少)
- Hepatomegaly(20%) +/- splenomegaly
- GI(25%, 比AL多)
- Nephro(most common involved, 90%, 比AL多)
- Nephrotic syndrome(80%, most common)
- 也可以只deposit在(BV) or (tubules basement membranes)而no obvious proteinuria but ESRD
- 可Type I, II, IV RTA, NDI
- (Rare)可intratubular casts formation similar to light chain cast nephropathy!!!
- 常常ESRD
- Tx
- Tx of underlying
- Colchicine 0.6-2.0mg/d
- 在FMF中有evidence; ↓disease progression, ↓proteinuria
- Cytotoxic and immunosuppressive agents and biologic agents
- Steroid, Endoxan, MTX, AZA, anti-TNFα, anti-IL6, anti-IL1...
- Dimethylsulfoxide(DMSO)
- anti-amyloid activity
- Insufficient evidence
- For renal amyloidosis
- 可Renal transplantation
- Graft survival is similar to general population
- 20-33% recurrence renal amyloidosis after transplantation but graft loss due to amyloidosis is uncommon
- 可Renal transplantation
- 註:eprodisate(failed)
-
Dialysis amyloidosis(Aβ2M)
- β2-MG(傾向堆積於osteoarticular structures)
- β2-MG是MHC I的component, 正常被glomerulus過濾後被proximal tubules幾乎全再吸收並代謝; 另外使用low-biocompatible membrane也會促進β2-MG產生
- Assuming steady β2-MG generation in a 70 kg anuric individual, net yearly β2-MG retention is 111g(low-flux), 97g(high flux), 77g(short daily HD), 53g(NHD), and 51g(short daily HF)
- Risk factors
- Loss of residual renal function
- Low flux HD
- Bioincompatible AK
- Long duration of HD
- Not ultrapure dialysate(?)
- 因為身體比較會發炎
- S/S
- Triad
- Shoulder pain(大多前外側, bilateral; abduction/night/supine/undergoing HD(=NHD最痛XD...) 會較痛; sit up or stand up較不痛)
- Scapulohumeral periarthritis(AL也可)
- Rotator cuff infiltrations
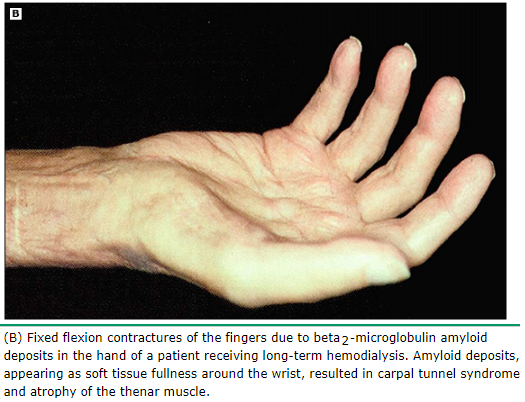
- Carpal tunnel syndrome
- 大多AVF/AVG那隻手較痛, 因為steal syndrome
- Hand flexor tenosynovitis(可fixed flexion contractures)
- Carpal tunnel syndrome(with atrophy of the thenar eminence) + Hand flexor tenosynovitis = amyloid hand
- Shoulder pain(大多前外側, bilateral; abduction/night/supine/undergoing HD(=NHD最痛XD...) 會較痛; sit up or stand up較不痛)
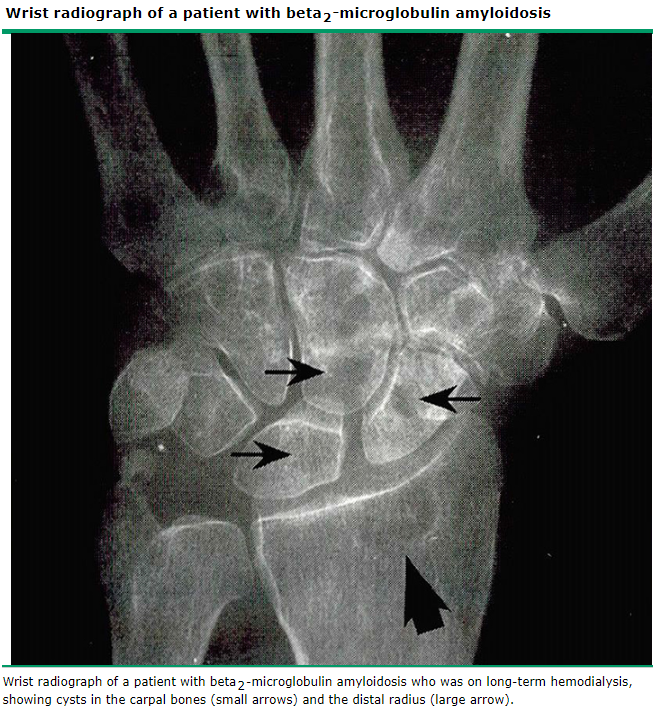
- Multiple(increase in number over time), rapidly(比brown tumor(secondary hyperparathyroidism)快) enlarging bone cysts(可導致pathologic fracture, 尤其weight-bearing area(like femoral neck))
- 最常在carpal bones, 但其他地方也可有
- Triad
- β2-MG(傾向堆積於osteoarticular structures)
-
Destructive spondyloarthropathy(β2-MG depositions之後-->macrophages phagocytosis-->inflammation)
- 可loss of the intervertebral disk space with erosion of the adjacent vertebral endplates(D/D infectious diskitis)
-
GI
- 最常在colon, 但tongue(macroglossia), esophagus, stomach, intestine也可以有
-
Others(rare)
- 心,肺,肝脾
-
Diagnosis
- 抽β2-MG沒有意義, 因為high level不代表有Aβ2M; Abdominal fat pad aspiration也沒用(why? uptodate沒解釋, 其原文:Abdominal fat pad aspiration is not useful to diagnose DRA)
- 可看X ray of carpal bones
- 可用echo看shoulder joint
- 可看CT, MRI of axial bones, shoulder joints, tendons
- 可看Scintigraphy with radiolabeled β2-MG or serum amyloid P component
-
Tx
- Renal transplantation
- After renal transplantation
- Amyloid deposition↓ soon
- Bone cysts resolve slowly
- Destructive spondyloarthropathy continues to progress !!
- After renal transplantation
- If HD kept
- Biocompatible high-flux AK, use β2MG adsorbent column
- Ultrapure dialysate
- Consider HDF
- Increase HD duration and frequency; consider SDHD or NHD
- If PD kept
- There are insufficient data to recommend a change in the dialysis modality
- Doxycycline 100mg QD(inhibits amyloid formation and accumulation)
- Reference:Benefit of doxycycline treatment on articular disability caused by dialysis related amyloidosis. (2013 Amyloid.)
- Use in 3 Pts
- Significant ↓articular pain, ↑passive and active movements though MRI showed no change of amyloid deposits
- Use in 3 Pts
- Reference:Benefit of doxycycline treatment on articular disability caused by dialysis related amyloidosis. (2013 Amyloid.)
- Consider OP(=清一清amyloid...)
- for shoulder pain
- Arthroscopic or open surgery to remove synovium(infiltrated by amyloids)
- for carpal tunnel syndrome
- Debridement of the hypertrophied synovium(infiltrated by amyloids)(不能只是transection of the transverse carpal ligament)
- for bone cysts
- Curettage and bone grafting of amyloid cysts
- 可relieve pain and prevent pathologic fractures
- Curettage and bone grafting of amyloid cysts
- for pathologic fractures
- Prosthetic joints
- for shoulder pain
- Renal transplantation
-
Hereditary amyloidosis
- Transthyretin(TTR; prealbumin)........一大堆
- S/S
- 多involve neuro +/- cardiac
- 可renal involvement, 不過要看是哪種depositions
- Transthyretin(TTR; prealbumin), fibrinogen A alpha chain(易recur if renal transplantation), lysozyme, apolipoprotein A-I (AApoAI) and A-II (AApoAII), and gelsolin (AGel)會堆積在kidney
-
Senile amyloidosis
- Transthyretin(prealbumin), ANP(可isolated atrial depositions)
- S/S
- 多involve cardiac(主), GI; 可lung(alveolar deposits); 可carpel tunnel syndrome
- Very rare renal involvement
-
Organ specific amyloidosis(due to locally produced proteins, 可isolated skin, brain, eye, heart, trachea, lung, kidney, GI, pancreas, liver, GU depositions...)
- Usually benign and surgical excision may be the only treatment needed
- 其中會renal amyloidosis者
- Apolipoprotein A-IV (AApoAIV) amyloidosis
- 沒找到genetic mutations
- 堆積在renal medulla(mostly peritubular and interstitial) and spare the cortex-->CKD/ESRD but trace proteinuria
- Leukocyte cell-derived chemotaxin 2-associated (ALECT2) amyloidosis
- 好發於西語裔(Hispanic/墨西哥裔, 美國病例>80%)、美洲原住民、Punjabi、埃及人; 東亞與純歐洲白人極罕見
- 堆積在kidney(主要堆積在cortical interstitium, with variable glomerular and vascular involvement) and liver
- CKD/ESRD(40% ESRD) and proteinuria but nephrotic syndrome is uncommon
- 非AL分型以laser microdissection/mass spectrometry確證並分型為準〔PMID 28828707〕
- Apolipoprotein A-IV (AApoAIV) amyloidosis
4.Diagnosis#
- MM surveillance(IFE, EP, serum free light chains, urine light chains)
- plasma cell dyscrasia 僅為必要條件,不足以單獨診斷 AL;須組織證實澱粉樣沉積並經分型(質譜或免疫)後方可診斷
- 最好還是有pathology
- 只有MGUS不能下診斷..., 因為MGUS有3-5% prevalence if age >50 y/o; 有(MGUS+Amyloidosis者)10%是non-AL type !!!
- 有些Hereditary amyloidosis也會monoclonal gammopathy
- plasma cell dyscrasia 僅為必要條件,不足以單獨診斷 AL;須組織證實澱粉樣沉積並經分型(質譜或免疫)後方可診斷
- Infection/AIR surveillance(要診斷AA還是需要biopsy)
- Including CRP, ESR(also for monitoring)
- very unusual to have AA amyloidosis with a normal ESR and CRP
- Including CRP, ESR(also for monitoring)
- FH, TTR/genetic study
- Biopsy
- 若覺得是systemic amyloidosis則abdominal fat pad biopsy為first line(not in dialysis amyloidosis), 因為不會有什麼complications
- Procedure:肚臍旁10cm, 10ml syringes with 16G needle, 取30mg fat
- Sensitivity/specificity→ 見上方病理段Congo red
- Organs(Kidney, liver, rectum, salivary glands, skin, bone marrow...)
- Biopsy確診amyloidosis後, tissue應拿去跑質譜儀分辨是哪種amyloid (Laser dissection of the tissue followed by tandem mass spectrometry-based proteomic analysis) (若只用immunohistochemistry(可染κ and λ light chains(sensitivity不好, 因為如上述常是λ light chains的"variable" area), transthyretin, and SAA, 但會false(+) and false(-)) and immunofluorescence(染κ and λ light chains)有可能無法分辨)
- Immunoelectron microscopy(immunohistochemistry + EM)好像還可以, 可當作質譜儀的alternative
- 應小心比較IHC, IF(+)處是否和LM, EM堆積處相同
- 若覺得是systemic amyloidosis則abdominal fat pad biopsy為first line(not in dialysis amyloidosis), 因為不會有什麼complications
- 核醫(ATTR-CM 非侵入確診): 99mTc-PYP/DPD 骨顯像(Gillmore 2016, Circulation; PMID 27143678):心肌攝取 Grade 2–3 且血清/尿免疫固定與游離輕鏈皆正常時 PPV 100%,可免心肌切片確診;若有單株蛋白仍須切片排除 AL
- Serum amyloid P component (SAP)(SAP會bind amyloid) scintigraphy
- Sensitivity:90% for AA(比AL更sensitive) and AL amyloid, 48% for hereditary transthyretin-related (ATTR) amyloidosis; Specificity: 93% in all three conditions
- Cardiac amyloidosis sensitivity差
- Potential infection risk(因為SAP from blood donors)
- EKG, CE, pro-BNP, TTE(speckled appearance), U/A, UPCR, Cre, BUN, Alb, LFT, abdominal echo, PT, PTT(if abnormal bleeding), NCV, EMG(不過若是small fiber neuropathy, NCV, EMG會(-))