Anti-GBM disease
Data from uptodate
- Pathogenesis and diagnosis of anti-GBM antibody (Goodpasture's) disease
- Treatment of anti-GBM antibody (Goodpasture's) disease
1.Pathogenesis#
- Ab(多IgG1 or IgG3; 但也可以是IgA or IgM in rare cases) against NC1 domain of the α-3(多; 不過也有Ab打α-4(少) or α-5(次) or ...) chain of type IV collagen (alpha-3(IV) chain)
- α-3主要在alveolar BM and GBM, 次之為renal TBM(所以也會有TIN), 再來可在choroid plexus, cochlea and retina偵測到
- 註:回思Alport's syndrome主要是 α-5, 所以若Alport's syndrome做完腎移植, 可能產生anti-GBM disease(但其Ab是打GBM的α-5 chain), 所以一般commercial kit of anti-GBM Ab未必驗得出來
- 不過study也發現autoreactive T cells佔pathogenesis中一大角色
2.Epidemiology#
- <1/100W
- 很少見, 西方也少見, 東方更少見
- Older children~any age adults都可有, 但<30 y/o比較會合併有pulmonary hemorrhage(Goodpasture's syndrome), >50 y/o較多isolated GN; 年輕人♂多一點, 老人♀多一點
- 和HLA DR15 and HLA DR4 and HLA DR2......相關
- HLA 關聯(常考)
- 易感/風險: HLA-DRB1*15:01(=DR15/DR2)(70-80%病人帶有), HLA-DR4
- 保護: HLA-DRB1*01(DR1) 與 HLA-DRB1*07(DR7)
- 誘發因子(次發成因考點): 吸菸(↑肺泡通透性→肺出血)、碳氫化合物有機溶劑/金屬粉塵、肺部感染、體液過負荷、ESWL或腎外傷(釋出GBM抗原)、Alemtuzumab(anti-CD52)治療後
- 標靶抗原: type IV collagen α3 chain的 α3(IV)NC1 domain
- HLA 關聯(常考)
3.S/S#
- As RPGN(anti-GBM disease大多acute, abrupt!!, 當然也有不典型insidious onset的...), 以nephritis為主, 少nephrotic range proteinuria
- 但也有一些atypical anti-GBM disease, 這些人大多血中測不到anti-GBM Ab, 也不會有alveolar hemorrhage, 雖然renal biopsy會發現bright linear IgG deposition along the GBM, 但nephritis沒有很嚴重也不會有crescents
- 50%alveolar hemorrhage(不一定會hemoptysis, 懷疑的話考慮測DLCO or chest CT or BAL(可同時排除其他airway lesions and 做cultures)), 少數個案甚至以alveolar hemorrhage predominates
- 有沒有肺部表現要看肺部抗原有沒有被表現出來, 也就是說肺部有被破壞者容易有肺部表現, 如smoking(主因), infection, 毒品/toxins(hydrocarbons...)inhalation
- 大多沒有如vasculitis的systemic S/S(如fever, malaise, BWL, arthralgia)
- 不過仍可以fever, malaise, arthralgia, abdominal pain; 但幾乎沒有neurologic nor GI S/S
4.Prognosis#
- 不治療>90%會死亡或ESRD
- Dialysis dependent AKI者很難recovery(來勢洶洶), 僅<10%會recover
- 也因此已經洗腎又沒有其他indication者, 不太做Tx(但也不一定)
- 和AAV不同!
- Remission者不太會recurrence(2%);腎移植時機(KDIGO 2021): 抗體陰轉後應至少等待 6 個月以上再移植,此時復發率極低〔PMID 34556300〕
5.Diagnosis#
-
Anti-GBM Ab(+, 不過小心commercial kit能驗到的有限, (-)不代表真的(-))
- Sensitivity, specificity不一定; atypical anti-GBM nephritis, post-transplantation in Alport's syndrome...可能都驗不出來
-
1/3 Pts也會有ANCA(+), 大多是P-ANCA, 甚至常常比anti-GBM Ab早出現, 扮演角色未知, 也可能真的會有AAV, 因為這些病人會有些vasculitis表現; 也有可能是先有AAV導致GBM epitopes露出來才產生anti-GBM Ab
-
Renal biopsy
- LM
-
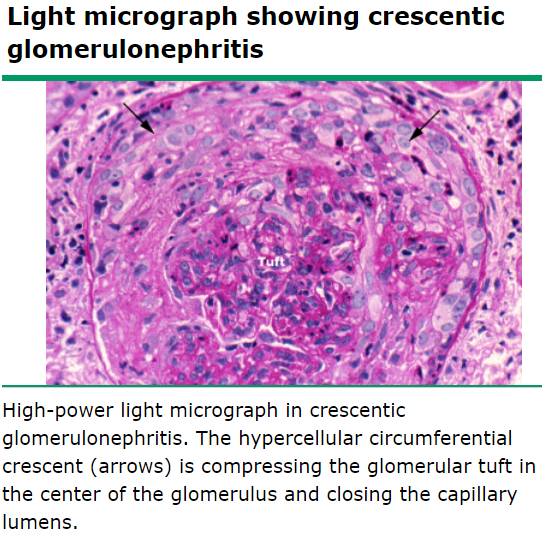
Crescent GN, 大多很嚴重且一致(不像AAV有好有壞)
Light micrograph showing crescentic glomerulonephritis
-
- LM
-
No vasculitis!(vs. ANCA)
-
也會有TIN, IFTA因為也有Ab也會攻擊TBM
-
Immunofluorescence
-
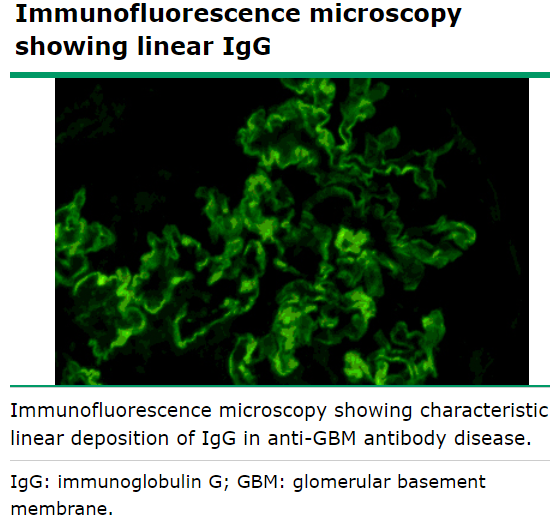
Linear deposition in the capillary walls==>anti-GBM disease(不過DM or SLE or fibrillary GN也有non-specific deposits(intensity沒anti-GBM disease高)=pseudolinear pattern)(Brenner說fibrillary GN是bandlike deposition而非linear nor granular pattern)
- DM:IgG/alb is nonspecifically absorbed onto the highly permeable glomerular capillary wall
- Fibrillary GN:IgG nonspecifically absorbed onto the fibrils
- 註:Fibrillary GN有些好像和anti-GBM disease相關
-
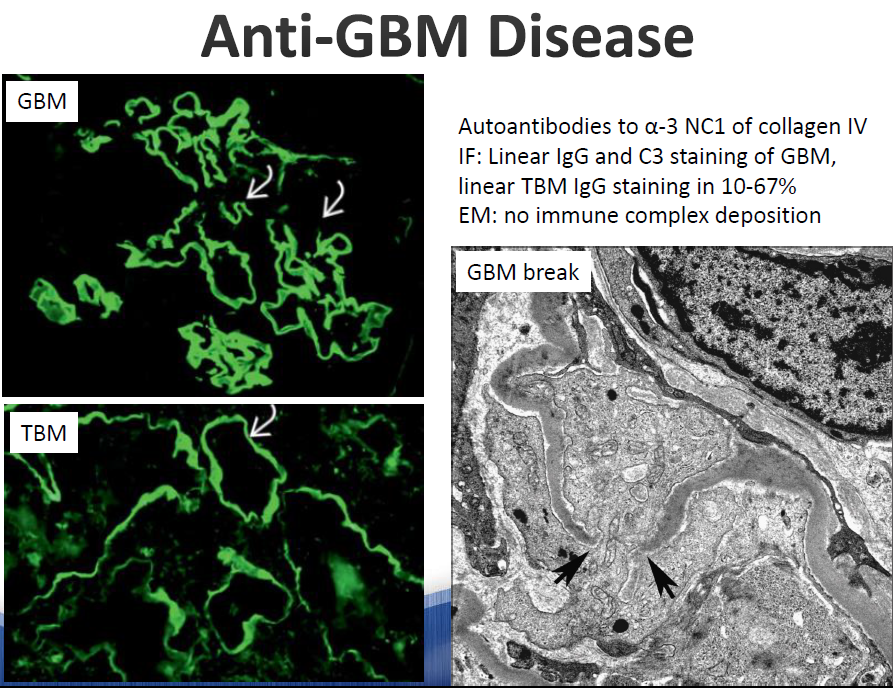
Anti-GBM disease主要是IgG(主要是IgG1, 但可以是IgG3)/C3(In rare cases, 可以是IgA or IgM) depositions over capillary walls +/- distal tubules BM(10-67%)(因為distal tubules BM也有alpha-3(IV) NC1)
Immunofluorescence microscopy showing linear IgG
-
Anti-GBM Disease
-
EM
Electron micrograph in crescentic glomerulonephritis
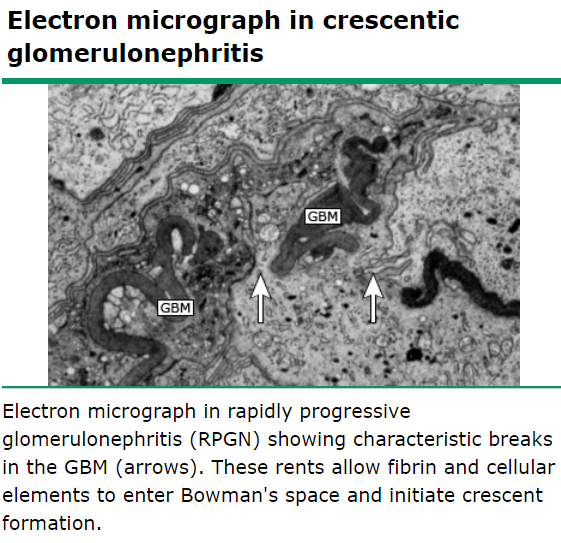
- No electron dense depositions(因為不是immunocomplex)
6.Tx#
- Stop smoking
- Baktar for PJP prophylaxis if indicated
- 治療適應症與指引(KDIGO 2021; PMID 34556300): 凡懷疑/確診 anti-GBM 即應「緊急啟動 Endoxan+高劑量類固醇+血漿置換」;唯一例外不建議常規治療者必須【同時滿足三項條件】:(1) 發病即依賴透析、(2) 腎切片 100% cellular crescents 或全面硬化、(3) 毫無肺出血證據〔PMID 34556300〕
- 若有肺出血(即使需透析)、尚未透析、透析但極急性仍有恢復機會、或伴隨 AAV(雙陽性)者均應全力積極治療
- 雙陽性(ANCA + anti-GBM)考點:急性期腎生存率介於兩者之間(ANCA alone > 雙陽性 > anti-GBM alone);抗體陰轉後仍具 AAV 高復發傾向,故必須遵照 AAV 指引接受長期維持治療〔PMID 15954926; PMID 34556300〕
- DFPP/TPE + immunosuppressions
- DFPP/TPE(見-Therapeutic apheresis-Goodpasture's disease(anti-GBM))
- 處方量每次1.0-1.5 plasma volume(PV, 約4L), QD/QOD(最好QD)洗≧14天, 到Ab測不到且clinical S/S(尤其pulmonary hemorrhage)改善
- 置換液以 5% albumin 為主; 若有肺出血、活動性出血、或48-72hr內剛做腎切片, 結尾須補 FFP 1-2L 以免凝血因子耗竭
- Monitor anti-GBM Ab QW under DFPP; then Q2W*2 if titer(-), then Q1M for 6M
- 處方量每次1.0-1.5 plasma volume(PV, 約4L), QD/QOD(最好QD)洗≧14天, 到Ab測不到且clinical S/S(尤其pulmonary hemorrhage)改善
- Ab level和disease activity相關性高(和AAV不同)
- 不過Brenner(p1429):Circulating anti-GBM antibodies are present in more than 90% of patients although the antibody titer does not always correlate well with the manifestations or course of either the pulmonary or renal disease
- 若洗DFPP者有嚴重感染, 可考慮補IVIG(0.1-0.4g/kg)
- DFPP/TPE(見-Therapeutic apheresis-Goodpasture's disease(anti-GBM))
- Immunosuppressions
- Pulse steroid 15-30mg/kg/d, up to 1g/d for 3 days; then Predonine 1mg/kg/d, up to 60-80mg/d, taper gradually to 20mg/d after remission(大多3W左右開始taper), 維持20mg/d至6W, gradually taper off over the next 6-9M
- Consider Nystatin, Gaster/PPI, Ca/vitamin D for prolonged steroid use
- Endoxan 2mg/kg/d for 2-3M
- 若Ab titers仍(+) after上述治療(約3M), 考慮繼續使用[(Predonine alone) or (predonine+AZA(1-2mg/kg/d)) or (predonine + MMF 2g/d)] for another 6M
- 維持治療(KDIGO 2021): 單純 anti-GBM 疾病復發罕見(0-6%),抗體陰轉後不需長期維持免疫抑制;但合併 ANCA(+)雙陽性者,須按 AAV 指引接受長期維持治療〔PMID 34556300〕
- Pulse steroid 15-30mg/kg/d, up to 1g/d for 3 days; then Predonine 1mg/kg/d, up to 60-80mg/d, taper gradually to 20mg/d after remission(大多3W左右開始taper), 維持20mg/d至6W, gradually taper off over the next 6-9M