MCD
1.MCD#
-
Primary FSGS<->MCD a spectrum of diseases?(有時候是FSGS沒biopsy到; 尤其FSGS多由juxtamedullary glomeruli開始sclerosis==>superficial biopsies可能miss)
- but Tx response different and prognosis different and elevated circulating soluble urokinase-type plasminogen activator receptor (suPAR) in primary FSGS
- 不過有些可能真的是?如tip variant?
-
Histology
- Light microscopy:normal(but enlarged glomeruli(why?) may be observed)
- 因為nephrotic syndrome, proximal tubules可有lipid droplets; proximal tubules也可flattening(simplification)
- Immunofluorescence microscopy:absence of immune deposits(no complement nor immunoglobulin deposits)
- 可有non-specific scattered (focal and segmental) IgM, C3 deposits at mesangial area(intensity不強) but EM不會有electron dense deposits(有的話應有IgM, C1q nephropathy的成分(見-MCD variants))
- 之所以要分出IgM nephropathy因為其預後比較差
- 可有non-specific scattered (focal and segmental) IgM, C3 deposits at mesangial area(intensity不強) but EM不會有electron dense deposits(有的話應有IgM, C1q nephropathy的成分(見-MCD variants))
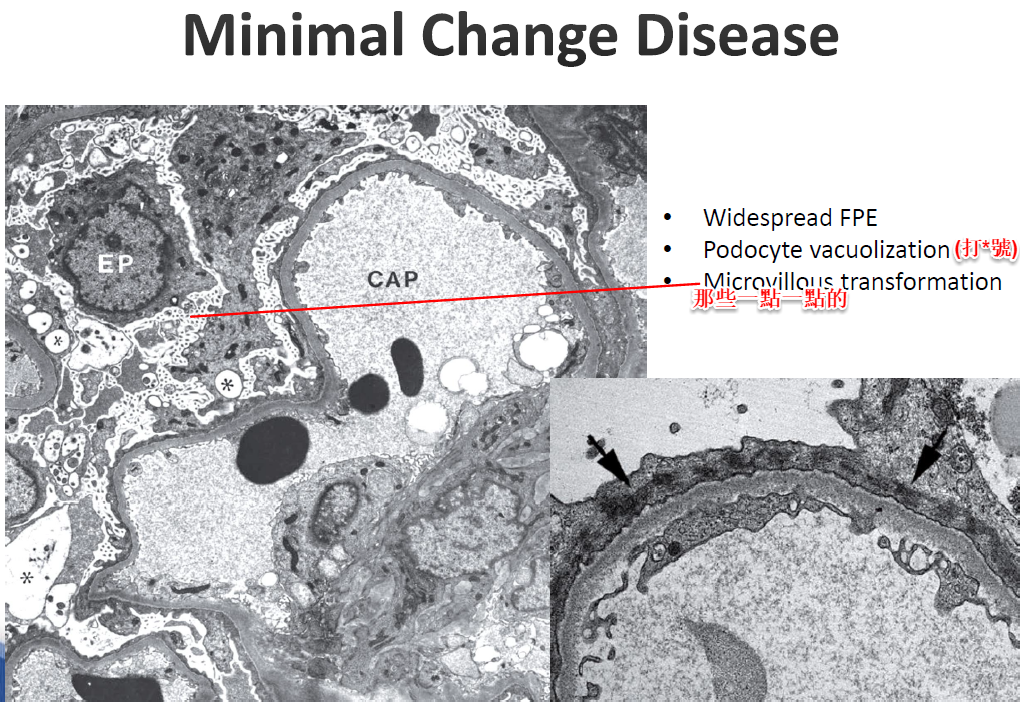
- EM:diffuse foot process effacement(retraction, widening, and shortening of the foot processes), podocyte vacuolization, microvillous transformation

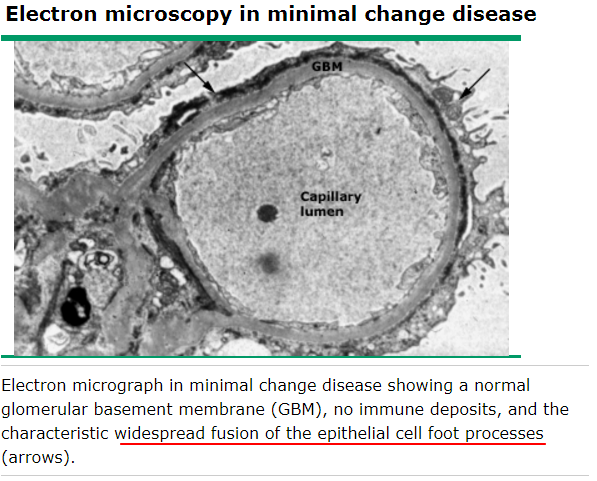
- Vacuolization來自於吸收的proteins and lipids
- Light microscopy:normal(but enlarged glomeruli(why?) may be observed)
-
Pathogenesis
- T cell dysfunction?(indirect evidence: atopic Pts, HL more MCD; 感染measles可能使MCD remission(an infection known to modify cell-mediated immunity)
- Lymphokines related? IL-13?
- B cell dysfunction與自體抗體突破:
- 【重大病理觀念更新】Hengel等(NEJM 2024; PMID 38804512):證實 MCD 實為以足細胞 slit diaphragm 關鍵蛋白 nephrin 為標靶之自體抗體疾病(成人活動期 44%、未治療活動期高達 69% 陽性),效價直接反映疾病活動度,並合理解釋抗 B 細胞治療(Rituximab)之顯著療效〔PMID 38804512〕
- Diminishes the anionic properties of the GBM(pathogenesis?)-->loss Alb
- 即↓charge selective property of GBM
- Genetic defect(heredity MCD is noted in 近親交配)
- T cell dysfunction?(indirect evidence: atopic Pts, HL more MCD; 感染measles可能使MCD remission(an infection known to modify cell-mediated immunity)
-
Epidemiology
- <10 y/o 的 idiopathic nephrotic syndrome 70-90%是 MCD
- 不過<1 y/o or >6 y/o仍較少見(所以常見於1-5 y/o), 所以有些專家在治療前會biopsy確診
- Vs. PSGN(常見於5-12 y/o)
- 10-18 y/o 的 idiopathic nephrotic syndrome 50%是 MCD
- Adult nephrotic syndrome:10-15%是MCD(decreasing in recent years with increasing FSGS)
- Male, Asian, white比較多
- <10 y/o 的 idiopathic nephrotic syndrome 70-90%是 MCD
-
Exclude
- I(rare):HCV(MPGN, cryoglobuline type II多, 可MCD, collapsing FSGS, MGN, IgAN, TMA, TIN, fibrillary GN, immunotactoid GN(?...)), syphilis(MGN>MCD), HIV(多collapsing FSGS, 可MCD, cryoglobulinemia/MPGN/lupus like GN, IgAN), mycoplasma(可MCD, MPGN), TB(多amyloidosis, 可MCD, collapsing FSGS, IgAN), Ehrlichiosis(tickborne), Lyme disease, Echinococcus(絛蟲)
- I:allergy related?(30% MCD Pts有allergy(含food allergy); 有些report記載給予oligoantigenic diet 可remission!; 所以和食物, 花粉, 某些植物(常春藤, 橡木...), 塵蟎, 蜜蜂叮咬...有關); many AIR(association); HSCT/GVHD(比MN早發生)
- M(degree of proteinuria大多和malignancy的嚴重度成正比):HL(0.4% Pts have MCD(其實也很少...); Brenner(p1804):The nephrotic syndrome occurs early, often preceding the diagnosis of lymphoma by several months), NHL, leukemia, thymoma; solid cancers很少見(solid cancers多MGN)
- M:NSAID(most common cause of secondary MCD)(MCD>MGN; AIN, pre-renal), gold(MGN>MCD), penicillamine(MGN>MCD), Lithium(MCD, FSGS, cTIN, NDI), Interferon(MCD/FSGS, 也可以ATN, TMA), Penicillin/beta-lactam/rifampin(多AIN; beta-lactam可ATN, MCD; rifampin類似NSAID), Sulfasalazine and 5-ASA, Aredia(MCD/FSGS) and other bisphosphonate(Zometa也可ATN), tamoxifen(MCD), anthracyclines(doxorubicin, daunorubicin...可MCD, FSGS(因為會傷害podocytes))
- C:PCKD(association),...?
-
S/S
- Nephrotic syndrome, 常忽然發生(over days~1W) after an infection/URI(其他GN的proteinuria大多以gradual increase over weeks to months表現, 只有primary MCD or primary FSGS會abrupt onset)
- 大多Alb<2, TP 4.5-5.5 g/dL
- 一樣會increased infection(因為IgG仍會↓, 雖然比Alb↓少) and thrombosis
- Adults(尤其>40y/o)比較會ischemic AKI(因為dehydration??), HTN, microscopic hematuria; 小孩比較不會
- U/A:adult多有microscopic hematuria(但RBC似乎都少少的); child則20-25%有microscopic hematuria
- 不過Brenner(p1296):Microscopic hematuria is seen in less than 15% of patients
- 所以MCD是唯一一個不太有microscopic hematuria的, MN(50%)和FSGS(50%, even gross)其實都還是會有microscopic hematuria
- GFR可因為foot process fusion本身decreases the filtration slit frequency而下降30%使Cre變成1.3~1.4X(!!), 但未必有AKI且acute renal failure is rare
- 所以MGN也可以因此↓GFR?
- Nephrotic syndrome, 常忽然發生(over days~1W) after an infection/URI(其他GN的proteinuria大多以gradual increase over weeks to months表現, 只有primary MCD or primary FSGS會abrupt onset)
-
Diagnosis
- <10 y/o 可先try steroid; 若steroid resistant-->biopsy
- Adult要biopsy(尤其>16 y/o)
- 有時難和FSGS分(尤其老人家), 因為The aging kidney commonly shows obsolescent glomeruli along with vascular lesions and interstitial fibrosis==>似FSGS
- 不過aging多focal and global(not segmental)(=FGGS) & 少"collapsing" or "tip" lesions(此二者favor FSGS)
- if focal and segmental IgM deposits(不常見但specific to FSGS)
- 有時難和FSGS分(尤其老人家), 因為The aging kidney commonly shows obsolescent glomeruli along with vascular lesions and interstitial fibrosis==>似FSGS
- 舊:No specific Ab → 新:Hengel等(NEJM 2024; PMID 38804512):成人MCD約44%(未治療活動期達69%)可測得循環anti-nephrin自體抗體,效價與疾病活動度相關,緩解期下降或轉陰〔PMID 38804512〕
- 小心Minimal change variants:idiopathic mesangial proliferative glomerulonephritis; IgM nephropathy; and C1q nephropathy
- 見-MCD/FSGS variant
-
Tx:
- General:consider low-salt diet, diuretics, ACEI/ARB, pentoxifylline, statin
- Definition of response(remission definition和FSGS是一樣的)
- CR:Proteinuria<0.3g/day or UPCR<0.2
- PR:proteinuria reduction >50% with 0.3-3.5g/day; 也有人定義為<3.5g/day with normal serum albumin level
- 如果PR要懷疑是不是診斷錯誤, Ex:FSGS; 因為MCD is almost always an all-or-none disease
- Relapse:proteinuria regained to >3.5g/day after CR/PR
- Frequent relapse(FRNS, KDIGO 2021定義):半年內復發≥2次, 或12個月內復發≥4次
- Relapse大多within 1yr after steroid tapered or DC
- Steroid dependence:relapse under steroid or requirement of steroid to maintain remission(relapse within 2W after steroid withdraw)(vs. FSGS是<2M)
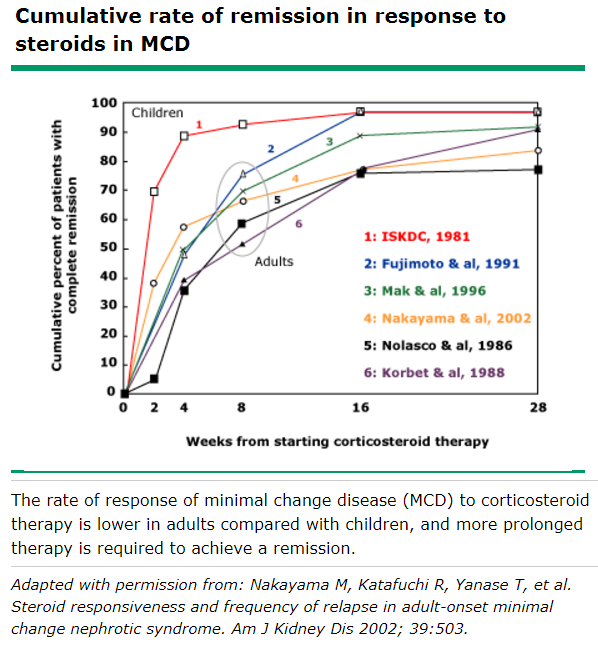
- Steroid resistance:little or no reduction in proteinuria(不到PR) after 16W(見最下圖, 16W仍無效就不太會有效) of adequate steroid Tx(小心:compliance不好, 劑量不夠, GI tract edema導致口服吸收不好, FSGS, MCD variants)
- 若尚未renal biopsy則應renal biopsy看到底是啥, 小孩子若4-8W steroid沒反應就應biopsy, 因為小孩子應4-8W就有反應
- Oral predonine 1 mg/kg/day(upto 80mg)(小孩:60 mg/m^2/d)for 3-4M(KDIGO 2021建議成人初發每日1 mg/kg(最多80mg)或隔日2 mg/kg(最多120mg),達CR後維持至少4週至最多16週,隨後緩慢減量≥24週〔PMID 34556300〕), then taper over the following 6M(太快taper常relapse)
- If steroid-sensitive + infrequent relapse + no obvious S/E of steroid的relapse
- 1 mg/kg/day(upto 80mg) for 1M followed by tapering over 1M(理由是這種relapse可能是來自acute infection(尤其viral infection) or allergic episode)
- If steroid-sensitive + frequent relapses + no obvious S/E of steroid的relapse
- Low dose predonine(Ex:15mg QOD); if needed, increase 5mg QW until stable remission(glucocorticoid dependent?)
- If steroid-sensitive + frequent relapses + 不想長期用steroid (這樣和steroid dependent不是一樣?)
- Endoxan > CsA(uptodate, grade 2B)(註:Endoxan和CsA remission rate差不多,但Endoxan longterm remission rate高得多(回思CNI類容易relapse...))
- Endoxan 2mg/kg/day for 8-12W(beginning after remission has been induced or maintained with prednisone)
- Strongly advise against repeated courses of cyclophosphamide(due to infectious, hematologic, and oncogenic complications)
- Endoxan總劑量建議<200mg/kg
- Repeat dosage就超過了...
- Endoxan總劑量建議<200mg/kg
- Strongly advise against repeated courses of cyclophosphamide(due to infectious, hematologic, and oncogenic complications)
- Endoxan 2mg/kg/day for 8-12W(beginning after remission has been induced or maintained with prednisone)
- Endoxan > CsA(uptodate, grade 2B)(註:Endoxan和CsA remission rate差不多,但Endoxan longterm remission rate高得多(回思CNI類容易relapse...))
- If steroid dependent or steroid resistant or still relapse after Endoxan or 不想用Endoxan(如:生育考量)
- CsA initial 4-5mg/kg/day, then keep trough level 100-200ng/mL for 18M(好久!!因為快速taper容易relapse), then taper to minimal effective dose; with low dose predonine(Ex:15mg QOD; 0.15 mg/kg/day)
- if in remission for >2 yrs-->taper (CsA and steroid)
- if no remission in 6M-------->CsA seemed no use-->DC CNI
- CsA PR/CR up to 80-90%, 但是relapses are very common after cessation of cyclosporine treatment(Brenner(p1297))
- S/E of CNI
- 見-Induction and maintenance immunosuppression in renal transplantation(also CNI toxicity)-8. S/E of CNI
- 註:Steroid dependent or steroid resistant Endoxan其實一樣可以用
- CsA initial 4-5mg/kg/day, then keep trough level 100-200ng/mL for 18M(好久!!因為快速taper容易relapse), then taper to minimal effective dose; with low dose predonine(Ex:15mg QOD; 0.15 mg/kg/day)
- If still refractory after Endoxan and CNI
- Rituximab 375 mg/m2 QW*1-4 或 1000mg D1+D15(KDIGO 2021已將RTX列為FRNS/SDNS的第一線steroid-sparing選項之一(與CNI、Endoxan並列), 多個RCT(Lancet 2011/2014、JASN 2018)證實可↓復發並停用steroid/CNI; 復發時可依CD19/CD20 B cell回升再給)
- Iijima等(Lancet 2014; PMID 24965823):RCT證實rituximab顯著延長FRNS/SDNS中位無復發期(267天 vs 101天,HR 0.27)〔PMID 24965823〕
- Iwabuchi/Takei等(Medicine 2014; PMID 25546674):成人SDNS使用單劑每6個月維持,24個月復發次數顯著下降(108次降至8次)〔PMID 25546674〕
- Rituximab 375 mg/m2 QW*1-4 或 1000mg D1+D15(KDIGO 2021已將RTX列為FRNS/SDNS的第一線steroid-sparing選項之一(與CNI、Endoxan並列), 多個RCT(Lancet 2011/2014、JASN 2018)證實可↓復發並停用steroid/CNI; 復發時可依CD19/CD20 B cell回升再給)
- Others:AZA/MMF:little evidence but maybe effective
-
Tx response/prognosis
- Spontaneously remission
- Early remission(within 3M):5-10% only
- 50% by 18M
- 70% by 36M
- ==>看起來會spontaneous remission but steroid可更快remission and maintain remission; 不治療有infection/thrombosis的可能性
- ESRD is rare and has only been reported in steroid-resistant cases(大多最後再biopsy是FSGS, 可能不是真的MCD?)
- Tx:
- Child 50% responds within 2W and near all within 1-2M
- Adult 50% response within 4W, 其他多於4M內CR(所以初始劑量才要維持3-4M!), 共有80-95%可CR, 但50-75%relapse, 10-25% frequent relapse, 25-30% steroid dependence, 5-10% steroid resistance(需要renal biopsy(若治療前沒做))
- Complete remission很快速(abrupt), 從開始有response到CR多2~3W, partial response少見(MCD is almost always an all-or-none disease)(如果PR要懷疑是不是診斷錯誤, EX:FSGS)
- Spontaneously remission