PSGN(Poststreptococcal glomerulonephritis)
1.Epidemiology#
- 5-12y/o(不過Brenner p1368是寫2-6 y/o) and >60 y/o 為high risk; ♂:♀=2:1
- <3 y/o 少PSGN
- vs. IgAN(<10 y/o少見), vs. MCD(常見於1-5 y/o)
- <3 y/o 少PSGN
- 以前一些old studies發現childs post-pharyngitis PSGN約5-10%, post-skin infection PSGN約25%
- 不過發生率decreasing; 因為(水中+Fluoride) and (streptococcus很容易治療; Abx開很兇的關係XD?)
- 此外, 大多沒有S/S(!!)
- PSGN和rheumatic fever很少一起發生
2.Pathogenesis#
- 1.Immunocomplex deposition(from circulating or in situ(主) formation...)
- 2.Molecular mimicry of GBM
- 3.Autoimmunities
- (1)Streptococcal neuraminidase會modify immunoglobulins, 使之變成autoantigens-->產生anti-IgG的Ab(所以容易有RA factors)
- (2)Other Ab
- 病患可有Anti-DNA Ab, Anti-C1q Ab, ANCA(infection類的GN常有一些ANCA(+)如IgAN, PSGN, chronic infections...), RA factors(RA factors 2/3 Pts有!; 因為是anti-IgG的IgM)
- 不過目前認為in situ formation of immunocomplex(streptococcal nephritogenic antigens堆積在GBM-->Ab結合-->injury)是主要機轉(vs. S.A. associated GN是circulating immunocomplex deposition為主)
- Potential antigens
- Nephritis-associated plasmin receptor (NAPlr)
- 為Glycolytic enzyme有glyceraldehyde-3-phosphate dehydrogenase (GAPDH) activity
- 有plasmin like activity(雖然明明叫plasmin receptor...)-->↑local inflammation
- Activate alternate pathway
- Streptococcal pyrogenic exotoxin B (SPE B)
- ↑chemotactic cytokines
- Activate alternate pathway
- 不過不同地區研究出來的Ag似乎不盡相同
- Activate alternate pathway所以C3↓↓
- Nephritis-associated plasmin receptor (NAPlr)
- Potential antigens
- 和host factors有關(如HLA-DRW4, HLA-DPA*02-022 and DPB1*05-01, and DRB1*03011...)
- 理論上是post-group A streptococcus(GAS) infection(GAS裡面有很多type, 每種也不太一樣), 但group C, group G也有案例
3.Pathology#
- LM
- Diffused proliferative GN with prominent endocapillary proliferation and numerous PMNs; Masson Trichrome stain可能可見small subepithelial hump-shaped deposits(red); crescent formation不常見; 常常有一些IN的changes(+/- TN)
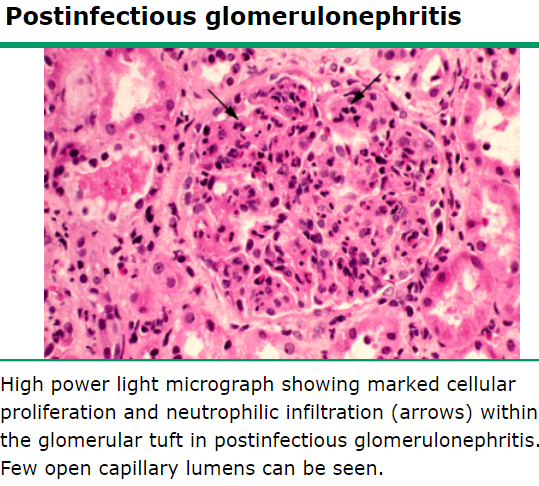
High power light micrograph showing marked cellular proliferation and neutrophilic infiltration (arrows) within the glomerular tuft in postinfectious glomerulonephritis. Few open capillary lumens can be seen.
- Immunofluorescence microscopy(見Glomerulus(immune)-PSGN)
- Diffused granular deposition of IgG and C3 within glomerular capillary walls and mesangiums(IgA, IgM and other complements也可以有, 但主要是IgG and C3)
- 但後期IgG會消失剩C3 !!(by Dr.林維洲)
- 若後期IgG沒消失則預後較差(較不會self-limited)
- IF三種pattern(好像不重要, 無關預後)
- Garland(capillary wall)
- 容易有nephrotic syndrome
- Starry sky(capillary wall + mesangium)
- Less severe(明明沉積最多?)
- Mesangial(mesangium)
- Resolving; LM此時多為isolated mesangial proliferation
- Garland(capillary wall)
- 但後期IgG會消失剩C3 !!(by Dr.林維洲)
- Diffused granular deposition of IgG and C3 within glomerular capillary walls and mesangiums(IgA, IgM and other complements也可以有, 但主要是IgG and C3)
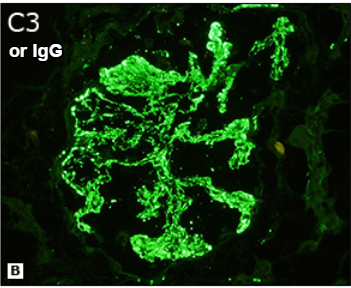
- Mesangial and subendothelial deposits and subsequent complement activation are responsible for the local influx of inflammatory cells(neutrophils), leading to a proliferative GN, active urine sediment, and a variable decline of GFR
- Subepithelial "humps" are responsible for epithelial cell damage and proteinuria, similar to MGN(但MGN的deposits很均勻規則和humps東一大坨西一大坨不一樣)
- 移除的比subendothelial慢, 所以proteinuria會比Cre, hematuria回復得慢(雖然移除比較慢, 但若晚期biopsy比較容易見到residual small subendothelial/mesangial depositions without subepithelial humps)
- 所以有5% Pts到nephrotic range的proteinuria...(→ 見§7 Course)
- 註:MPGN的DDD也可以有subepithelial humps
- 移除的比subendothelial慢, 所以proteinuria會比Cre, hematuria回復得慢(雖然移除比較慢, 但若晚期biopsy比較容易見到residual small subendothelial/mesangial depositions without subepithelial humps)
- EM
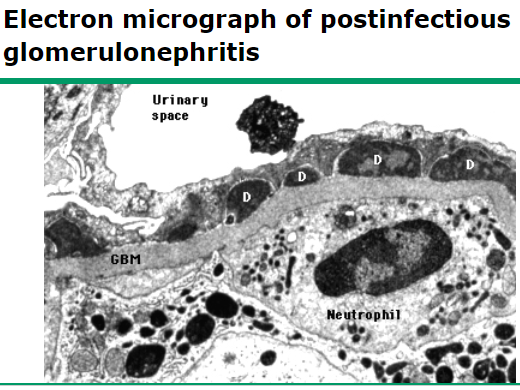
Electron micrograph of postinfectious glomerulonephritis
D=Deposits(subepithelial)=humps
4.S/S#
- Nephritis syndrome(1-3W(average 10d) after pharyngitis and 3(2)-6W after skin infection)
- From asymptomatic(most childs) to acute nephritis syndrome(but crescent GN is very rare)
- 可以macroscopic hematuria
- Lab
- Variable AKI但大多不用RRT
- Urine
- U/A
- as GN but常有pyuria(回思因為有許多neutrophils infiltrations?)
- 只有5% Pts有nephrotic range proteinuria(vs. S.A. associated GN為20% nephrotic syndrome)
- U/A
- Complements
- C3↓↓↓ in the first 2W then return to normal range within 4-8W
- 2M內C3應normal
- C4, C2也可以↓(不過多normal)
- 因為由上述pathogenesis可知alternative pathway為主
- C3↓↓↓ in the first 2W then return to normal range within 4-8W
- Cultures
- 25% skin or throat cultures(+)
- 但若有impetigo則cultures多(+)
- Streptozyme test(including Anti-streptolysin (ASLO), Anti-hyaluronidase (AHase), Anti-streptokinase (ASKase), Anti-nicotinamide-adenine dinucleotidase (anti-NAD), Anti-DNase B Ab)
- Post-pharyngitis 95%(+); post-skin infection 80%(+)
- 若只測ASLO要小心post-skin infection容易falsely negative(因為some strains of type 12 GAS不會產生streptolysin O; 此時測antihyaluronidase or anti-DNase B較好)也要小心若pharyngitis有用Abx也可能ASLO falsely negative
- 25% skin or throat cultures(+)
5.Diagnosis#
- 多不用renal biopsy, 見上述S/S
- 腎切片適應症(KDIGO 2021; PMID 34556300): PSGN 多自限不需切片,但出現以下警訊應切片以鑑別 MPGN/C3G/SLE/其他 IRGN:
- 補體異常: 發病時 C3 正常,或低 C3 持續超過 8-12 週未回升〔PMID 34556300〕
- 病程不符: 肉眼血尿 >3-4 週、少尿或 AKI >2-3 週未改善、需透析之重症 AKI
- 蛋白尿不退: 持續蛋白尿 >6 個月或腎病症候群(>5%)
- 無感染證據: 缺乏鏈球菌血清學或培養證據
- D/D: 見IgA nephropathy and HSP鑑別段;本質為免疫複合體型內皮增生性 GN
6.Tx#
- Abx if active infection or culture(+)
- 【重要觀念】抗生素治療活動性感染可根除細菌並防止菌株擴散與風濕熱,但無法縮短已發作之 PSGN 病程或減輕腎絲球損害〔KDIGO 2021; PMID 34556300〕
- Supportive care as AKI (限鈉水、利尿劑、降血壓)
- Crescent >30%時雖然沒有證據顯示immunosupressive Tx有效, 但大多還是會用pulse steroid之類...(不過crescent少見)
7.Course#
- 典型四步恢復時序:
- 利尿排鈉: 多於 1-2 週開始
- 血清肌酸酐回基線: 多於 3-4 週回到基線
- 補體 C3 完全回升: 4-8 週 (<2M) 回升正常(若 >8-12 週未回升為重要切片警訊,見 §5〔PMID 34556300〕)
- 鏡下血尿消失: 多於 3-6 個月消失(最晚 <1 年;蛋白尿消退較慢,可拖延 1-2 年)
- 小孩子的預後很好, >90%會recover; 大人可能有30-50%不會完全回復
- 但基本上之後都還是有secondary FSGS的可能性, 導致幾十年後ESRD
- Brenner(p1332):An initial episode of acute renal failure is not necessarily associated with a bad prognosis; but the long-term prognosis of patients with PSGN is not as benign as previously considered.
- 很少recurrence, 可能是因為persistence of Ab to potential antigens
- vs. IgAN, MPGN