Summary of GN Tx
不同GN對開始治療的threshold不同, 因為outcomes/prognosis不同, 如下圖
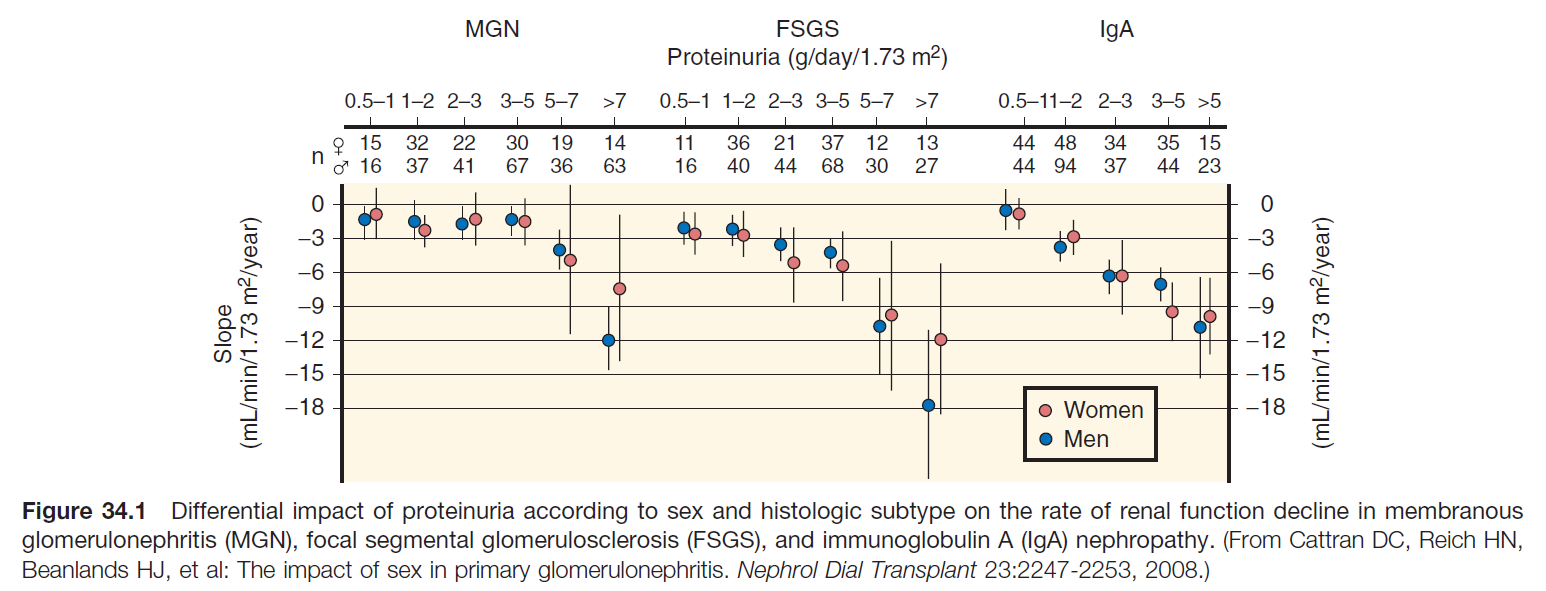
| Type of GN | For all |
|---|---|
| - Low-salt diet, diuretics, BP control(KDIGO 2024: standardized office SBP<120mmHg if tolerated, 至少<130/80), ACEI/ARB(+/- non-DHPCCB, Aldactone), Statin, Pentoxifylline, SGLT2i(蛋白尿性CKD/GN標準支持治療, eGFR≥20+蛋白尿即可用, 與DM無關; DAPA-CKD 2020、EMPA-KIDNEY 2022; KDIGO 2024 Grade 1A), consider PJP prophylaxis, consider anticoagulants(If 1.[(thrombosis risk factor(+) or (Alb<2g/dL)) + (HAS-BLED score≦4)], or 2.If (MGN+Alb<3g/dL+HAS-BLED score≦3)), 有些專家會用Aspirin in Pts with nephrotic syndrome and Alb 2-3g/dL and no other thrombosis risk factors and (low to moderate bleeding risk) | |
| - finerenone(非類固醇MRA; FIDELIO-DKD 2020/FIGARO-DKD 2021/FIDELITY統合: CV −14%、kidney −23%): T2D+CKD+albuminuria標準治療, 可與RAASi+SGLT2i併用(KDIGO 2024) | |
| - semaglutide/GLP-1 RA(FLOW, NEJM 2024): T2D+CKD主要kidney outcomes −24%, 已入KDIGO 2024 CKD指引(詳見Diabetic kidney disease(DKD)) | |
| - CNI:原則上用6M無效會停掉, 原則上多用≧1yr, 原則上taper是↓25% dosage Q2M | |
| - Consider Nystatin, Gaster/PPI, Ca/vitamin D for prolonged steroid use | |
| MCD | (Steroid-->Endoxan/CsA-->R-->MMF/AZA) 1.Initial - Oral prednisone 1 mg/kg/day(upto 80mg/d)(小孩:60 mg*m^2/d)for 3-4M(小孩可能不用這麼久僅1-2M), then taper over the following 6M(太快taper常relapse) 2.If steroid-sensitive + infrequent relapse + no obvious S/E of steroid的relapse - 1 mg/kg/day(upto 80mg) for 1M followed by tapering over 1M(理由是這種relapse可能是來自acute infection(尤其viral infection) or allergic episode) 3.If steroid-sensitive + frequent relapses + no obvious S/E of steroid的relapse - Low dose prednisone(Ex:15mg QOD); if needed, increase 5mg QW until stable remission(glucocorticoid dependent?) 4.If steroid-sensitive + frequent relapses + 不想長期用steroid (這樣和steroid dependent不是一樣?) - Endoxan > CsA(uptodate, grade 2B) - Endoxan 2mg/kg/day for 8-12W(beginning after remission has been induced or maintained with prednisone) - Strongly advise against repeated courses of cyclophosphamide(due to infectious, hematologic, and oncogenic complications) - Endoxan總劑量建議<200mg/kg - Repeat dosage就超過了... 5.If steroid dependent or steroid resistant or still relapse after Endoxan or 不想用Endoxan(如生育考量) - CsA initial 4-5mg/kg/day, then keep trough level 100-200ng/mL for 18M(盡量用久, 因快速taper容易relapse), then taper to minimal effective dose; with low dose prednisone(Ex:15mg QOD; 0.15 mg/kg/day) - If in remission for >2 yrs-->taper (CsA and steroid) - If no remission in 6M---------->CsA seemed no use-->DC CNI - 注:Steroid dependent or steroid resistant者, 再試一次Endoxan一樣可以用 6.If still refractory after Endoxan and CNI - Rituximab 375 mg/m2 Q6M - Others:AZA/MMF:little evidence but maybe effective |
| MCD/FSGS variant-Idiopathic mesangial proliferative GN | Nephrotic syndrome者,一線治療同 MCD/FSGS(口服 steroid,無效加 CNI) |
| MCD/FSGS variant-IgMN | 若表現 nephrotic syndrome,一線治療同 MCD/FSGS |
| MCD/FSGS variant-C1q nephropathy | Uptodate:There are no randomized trials that have evaluated the treatment of C1q nephropathy. Therapy involves treatment of the underlying light microscopic lesion (eg, MCD or FSGS) |
| FSGS | (Steroid-->CNI(也可一開始就用)-->MMF(不過有一些trials發現MMF效果不輸給CsA)-->?)(TPE/ CTLA-4 analogue/ACTH/LDL apheresis); cytotoxic agents/Rituximab偶多是steroid sparing agents且是第三線(after MMF)); 現代支持治療: SGLT2i(見For all)+sparsentan(FDA 2026/4核准第一個FSGS藥; DUPLEX主要終點eGFR slope未達(P=0.75)但蛋白尿−46%; 2026/8擴小兒) 1.Primary(not collapsing variant) with nephrotic syndrome - Naive - Predonine 1mg/kg/day(upto 60-80mg/day)(小孩:60 mg*m^2/d) for 8-16W(多8W開始taper), then tapering, 總duration看反應, 甚至可長達一年 - 若8W無效, 則taper and consider adding other drugs - Or CNI(MMF(1.5~2g/d for 6M or longer) if eGFR<30) +/- low dose Prednisone(≦15mg QD or 0.15mg/kg/d) for 12M if high risk of steroid toxicity(obesity or DM or severe osteoporosis or Age>70), then slowly tapering(↓25% CNI dosage Q2M) - Late relapse(>2M after DC steroid) after remission + no significant steroid toxicity - Use steroid as above - (Late relapse(>2M after DC steroid) after remission + significant steroid toxicity) or multiple relapse - CNI(MMF if eGFR<30) +/- low dose Prednisone for 12M - Steroid-dependent - CNI(MMF if eGFR<30) +/- low dose Prednisone - if failed-->MMF+low dose Prednisone - Consider Rituximab, cytotoxic agents(Endoxan(2-2.5mg/kg/d for 8W), Chlorambucil) - 和MCD不同, Endoxan在此種情形不是第一線!!(是第三線!!) - Steroid-resistant - CNI(MMF if eGFR<30)+ gradually taper Prednisone - No role of cytotoxic agents nor Rituximab(?) - Consider TPE if very high circulating permeability factors(基本上albuminuria也會很嚴重) + still severe disease(after adequate immunosuppressions) - Others - Abatacept(?, CTLA-4 analogue; 因為podocyte會表現CD80(B7-1)激活T cell); LDL apheresis(reduction in oxidized LDL and associated inflammatory cytokines ==>reduction in proteinuria); (ACTH); pirfenidone(↓fibrosis而↓GFR decline rate; evidence少) 2.Non-nephrotic range - Obs, 因為大多是secondary FSGS or 已經太晚期 3.Primary(collapsing variant, non-HIV) - 類似上述的steroid use, total 6M - If proteinuria >10g/day + Alb<2g/dL + preserved GFR, 則同時也用CNI - No evidence of cytotoxic agents(poor efficacy of with significant side effects) |
| Primary MGN | (steroid-->Endoxan/CNI-->Rituximab(MENTOR NEJM 2019; PMID 31269364:24M CR/PR 60% vs 20%優於CsA〔PMID 31269364〕; KDIGO 2021: moderate-high risk第一線, anti-PLA2R分層+3M/6M序列監測〔PMID 34556300〕; STARMEN 2021〔PMID 33166580〕; RI-CYCLO 2021〔PMID 33649098〕)-->MMF-->?(TPE, ACTH)) 分低中高risk - Low risk(<4 g/d & GFR normal for 6M):Obs - Moderate risk(4-8 g/d & eGFR≥60(KDIGO 2021) & (no S/S or edema controlled by diuretics)) for 6M - Pulse solumedrol 1g/day for 3 days(M1,3,5) + Predonine 0.5mg/kg/day(M1,3,5) + Endoxan 2-2.5mg/kg/day(M2,4,6) - or CNI+ steroid - High risk(>8 g/d or >3M (or GFR (below normal due to MGN) or (decreasing(r/o other causes) despite maximum non-immunosuppressive therapy over 3M)) - If severe S/S or Alb<2 or elevated Cre可能不用等3M - Tx基本上如moderate risk是一樣的, 不過若indication是declining renal function則CNI不是第一線 - Others:MMF(似乎只有東方人有效, 不過MN本來預後就是東方人較好(vs. LN)), Rituximab(或可當第一線?→2021後已是第一線), TPE, ACTH(?) 不過姜文智醫師經驗是 - 1.都治療, 沒有分risk, 因為spontaneous remission<10%(和國外data不同), 此外delayed Tx影響prognosis(NTUH data) - 2.先try steroid即可(0.5-1mg/kg/d), 2M沒達到PR則try Endoxan, 有則繼續steroid, 只用steroid治療可有70% response - 3.Rituximab有效, 但是也沒有比Endoxan或pulse steroid有效, 不過副作用少很多 |
| IgAN/HSP | (KDIGO 2025 IgAN/IgAV指引: 蛋白尿目標<0.5g/d、理想<0.3g/d; 有進展風險才加免疫治療) 1.For all: Na restriction, RAASi titrate至最大可耐受, SGLT2i(eGFR≥20, 1A), sparsentan(高風險持續蛋白尿者, 2023核准), statin, BP<120(standardized, 可耐受時) 2.仍有進展風險(UPCR持續>0.5-1g/g或eGFR下降)→Nefecon(targeted-release budesonide) 9M療程 或 減量全身性steroid(TESTING 2022: 0.4mg/kg/d, max 32mg/d); fish oil已非常規 3.RPGN或severe active histology(crescent/proliferation)→pulse steroid+Endoxan(0.5g/m2 Q1M*6), 可考慮TPE/DFPP if crescent 4.Isolated nephrotic syndrome+MCD pattern→Tx as MCD 5.Rituximab: KDIGO 2025 不建議常規用於IgAN(證據不足) 6.新興: iptacopan(2024/8加速核准)、atrasentan(2025/4)、sibeprenlimab(2025/11) |
| PSGN/IRGN | 1.PSGN - 主要是Supportive care - Abx if [S/S(+) or culture(+)] - 若crescent GN考慮用immunosuppressions(雖然沒有證據) 2.S.A. associated GN - 主要是Supportive care - Abx(因為是active infection) - No benefits of immunosuppression(且active infection不建議使用immunosuppressants) 3.IE related GN - Abx(因為是active infection) |
| MPGN | (基本上是Treat underlying; 但若是找不出原因(idiopathic)且較嚴重, 則看機轉來決定Tx) 1.Treat underlying如infection, AIR(自體免疫/免疫風濕), CLL, MM 2.If idiopathic - Immune complex-mediated - Indication of immunosuppression if nephrotic range proteinuria or HTN(?!因為type I MPGN若有HTN, 預後較差?) or decreased GFR or severe histologic change of renal biopsy or progressive under ACEI/ARB(over 3-6M) - No well studies(uptodate建議如下) - Nephrotic syndrome with near normal Cre - As FSGS:(steroid -> CsA) - (Decreased GFR or HTN) +/- nephrotic range proteinuria, without crescent - Steroid->Endoxan->Rituximab - RPRF +/- crescent - Steroid+Endoxan - Complement mediated(uptodate建議如下)(詳見專章TMA(TTP-aHUS and secondary)之補體媒介/aHUS段落) - Normal GFR + proteinuria <0.5g/day + hematuria - no specific Tx - If HTN or proteinuria >0.5g/day - ACEI/ARB - Severe proteinuria or nephrotic syndrome or decreased GFR(Not RPRF) - Ab related - no consensus; consider TPE, Rituximab, Eculizumab... - Factors deficiency or activating mutation in C3 - FFP infusion/TPE/Eculizumab - Unknown--->trial of plasma infusion (or Eculizumab?) - RPRF - Steroid + (Endoxan or MMF) +/- plasma exchange(尤其Factors deficiency or activating mutation in C3) - C3G / IC-MPGN 新藥: iptacopan(Fabhalta, 2025/3 FDA核准首個C3G標靶藥, APPEAR-C3G蛋白尿−35.1%〔PMID 41016405〕); pegcetacoplan(C3/C3b抑制劑; VALIANT, NEJM 2025, 蛋白尿相對降低68.1%〔PMID 41337715〕) |
| Cryoglobulinemia | 1.Cold avoidance and analgesics 2.Type I - Tx of underlying 3.Type II-III - If idiopathic - If mild to moderate manifestation - Colchicine(1-2mg/day) or low dose steroid(10-25mg/day, taper to <10mg/day by 6M if feasible) - if severe(any:severe digital ischemia/vasculitis, RPGN/nephrotic syndrome, GI vasculitis, pulmonary vasculitis, CNS vasculitis, severe neuropathy, heart failure - Rituximab(alternative:Endoxan) + rapidly tapered Steroid - 注:Rituximab打贏Endoxan - Add plasmapheresis (if life threatening or hyperviscosity syndrome) - If underlying(+) - Tx of underlying disease - If severe - Rituximab(alternative:Endoxan) + rapid tapered Steroid(用immunosuppression前應先治療HBV(Entecavir或TDF/TAF,持續至停免疫抑制後≥6-12M,Rituximab後≥12M) & HIV)(HCV相關者以DAA為基礎治療;嚴重血管炎/RPGN則DAA與Rituximab同步併用,不再延遲抗病毒) - 注:在HCV者, Rituximab一樣打贏Endoxan - Add plasmapheresis (if life threatening or hyperviscosity syndrome) - 注:TPE/DFPP studies多用在MPGN, neuropathy, arthralgia, ulcerating purpura - Uptodate建議:hyperviscosity syndrome, crescent GN, pulmonary hemorrhage, intestinal vasculitis, severe/refractory skin ulcers者併用TPE/DFPP |
| TMA | 詳見專章TMA(TTP-aHUS and secondary); Treat underlying + 支持治療(嚴格BP控制、透析); TTP→TPE(1-1.5X plasma volume QD)+steroid+rituximab+caplacizumab(2019核准); aHUS/complement-mediated→eculizumab/ravulizumab一線; drug/toxin-mediated→移除致病物 |
| LN | Class I/VI - supportive care Class II - supportive care; but if nephrotic syndrome, Tx as MCD/FSGS Class III/IV - Induction - (Endoxan or MMF) + steroid(+/- pulse); KDIGO 2024: 可在MMF+steroid上再加belimumab(BLISS-LN)或voclosporin(AURORA-1)組成triple therapy(第一線選項); obinutuzumab(2025/10 FDA核准, REGENCY)亦為新選項 - 若其中1種failed(no CR/PR at 6M), 則改另一種, 兩種都failed則改[(Rituximab) or (MMF+FK506)] - KDIGO 2024 反應定義: CR=UPCR <0.5 g/g 且 eGFR 穩定(基線 ±10-15%),於 6-12M 內達成;PR=UPCR 下降 ≥50% 且 <3.0 g/g;PERR ≤0.7 僅為 BLISS-LN 試驗終點切點,勿與 KDIGO CR 混用〔PMID 38182286〕 - 總療程: proliferative LN 誘導+維持總療程應 ≥36 個月(自誘導治療開始起算) - Maintenance: MMF 0.5-2g/d or AZA 2mg/kg/d (MMF 優於 AZA,復發較少) - Class III/IV + V: MMF+CNI+steroid multitarget 佳 - Class V: MMF+steroid 為一線,誘導無效換 CNI 或 Endoxan |
| AAV | (for GN-->[Induction by (Rituximab or Endoxan)+steroid]-->[Maintenance by (MTX or AZA or Rituximab); C-ANCA者似乎 maintenance by Rituximab較好]) 1.GPA/MPA - Tx if any S/S of "active" vasculitis - Induction - If not severe(無CNS vasculitis/progressive neuropathy, orbital pseudotumor, 心, pulmonary hemorrhage(只有pulmonary nodule不算severe), GN, GI involvement) - MTX(or rituximab) + steroid - If severe(有CNS vasculitis/progressive neuropathy, orbital pseudotumor, 心, pulmonary hemorrhage, GN, GI involvement) - (Endoxan + steroid(pulse if needed)) or (Rituximab + steroid(pulse if needed)); avacopan(C5aR inhibitor)曾獲KDIGO 2024建議可替代類固醇做remission induction,但其主試驗ADVOCATE已於2026-06-29被NEJM撤稿〔PMID 42377355〕,臨床使用需高度審慎 - 若Endoxan, Rituximab都resistance, 則try MMF - Baktar 1# QD until no cytotoxic agents and predonine ≤10mg/day - 注意MTX和Baktar不能一起用 - DFPP/TPE(KDIGO 2024: 不再常規; PLEX僅考慮於 SCr>3.4mg/dL、需RRT、SCr快速上升、DAH合併低血氧、或合併anti-GBM) - Maintenance(start after remission(多within 3-6M))[KDIGO 2021/2024建議常規維持至少18-24個月再極慢速taper(1年太短, 停藥後復發率高)(但high risk of relapse者(Ex:C-ANCA or persistent high titers or pulmonary involvement or upper airway involvement or nasal carriage of S.A.) =>2-3 yr, even indefinitely(尤其傷害嚴重身體無法容忍relapse者)), 但若已經永久ESRD, 因為免疫力↓, 所以多3-6M maintenance Tx即可] - 如果是drugs induced AAV不用maintenance - P-ANCA - MTX(with folic acid) or AZA(less relapse than MMF; 和LN的data相反...) or rituximab(data較少) - 有些專家傾向在low risk of relapse且身體狀況良好者不用maintenance Tx(因為P-ANCA比較少relapse) - C-ANCA - 用rituximab較好(less relapse than AZA) - 有些專家傾向用Rituximab if induction with remission by Rituximab; 用AZA if induction with remission by Endoxan; 少用MTX - If relapse during maintenance Tx - 看嚴重度, 若severe則需re-induction重來一次(之後的maintenance改藥-->and indefinite?); 若not severe則↑maintenance dosage - If relapse after completion of maintenance Tx - 看嚴重度, 若severe則需re-induction重來一次(之後的maintenance用同藥-->and longer duration/indefinite?); 若not severe則↑用之前maintenance的藥並longer duration 2.EGPA - Five-factor score(FFS) - >65 y/o, CV, GI, Cre>1.7, absence of ENT involvement(presence is associated with a better prognosis) - 一項一分 - Induction - Prednisone 0.5-1.5mg/kg/day(higher dose if organ involvement or more severe); pulse steroid 1g QD for 3 days if acute multiorgan involvement - taper over 12-18M after remission; 有一部分Pts可能會需要長期low dose prednisone(Ex:10mg/day), 若長期需要更高的steroid dose則要用其他藥物(AZA or MTX...) - 若無心肺腎CNS involvement, steroid可使93% Pts remission - Add on Endoxan if (CNS or 心 or FFS≧2)(increase survival vs. steroid alone); 有些專家覺得(FFS=0 but ANCA(+))也要用Endoxan, 因為ANCA(+)比較會腎, peripheral nerves involvement; Dosage as GPA/MPA, duration多6-12M - Add on (AZA or MTX) if (FFS=1 but not CNS nor 心 involvement) - AZA(2mg/kg/day) - MTX dosage as GPA/MPA - Maintenance Tx(主要是MTX or AZA) - 若induction有用Endoxan - Change to [(AZA)+ (tapering steroid)] - Or MTX - Or Arheuma(data少) 10-30mg/day - 若induction有用(AZA or MTX) - 繼續用? - 若需要prednisone > 10mg/day to keep remission - change to [(MTX or AZA)+ (tapering steroid)] - Or Arheuma(data少) 10-30mg/day - Second line - MMF, Rituximab, Hydrea, IVIG, plasma exchange(if DAH or RPGN), Omalizumab, Anti-IL-5, Interferon-alpha... |
| Anti-GBM disease | (若要Tx-->induction by DFPP+Endoxan+Steroid-->then consider [(steroid) or (AZA+steroid) or (MMF+steroid)] if anti-GBM Ab still(+)) 1.Stop smoking 2.Indication(any) - Pulmonary involvement - Renal involvement(尚未洗腎) - Renal involvement[已洗腎, if very acute(因為不確定會不會回復) or 伴隨AAV(ANCA(+)+vasculitis S/S(+)) or younger Pts(比較可容忍immunosuppressions, 也拚個機會)] - 僅(已經洗腎且(其實已經洗腎大多不會recovery, 僅8% renal survival at 1yr) + 看起來renal function不會回復(可看histology的chronicity) + 沒pulmonary involvement + 未伴隨AAV)不做治療 3.若要治療(DFPP/TPE + immunosuppressions) - DFPP/TPE(見-Therapeutic apheresis-Goodpasture's disease(anti-GBM)) - 每次 1.0-1.5 plasma volume(約4L) QD/QOD(最好QD)洗≧14天, 到Ab測不到且clinical S/S(尤其pulmonary hemorrhage)改善 - Monitor anti-GBM Ab QW under DFPP; then Q2W*2 if titer(-), then Q1M for 6M - 因為Ab level和disease activity相關性高(和AAV不同) - 若最近有renal biopsy or 有pulmonary hemorrhage or 有bleeding tendency, 則用TPE(或部分使用TPE) - 若洗DFPP者有嚴重感染, 可考慮補IVIG(0.1-0.4g/kg) - Immunosuppressions - Pulse steroid 15-30mg/kg/d, up to 1g/d for 3 days; then Predonine 1mg/kg/d, up to 60-80mg/d, taper gradually to 20mg/d after remission(大多3W左右開始taper), 維持20mg/d至6W, gradually taper off over the next 6-9M - Consider Nystatin, Gaster/PPI, Ca/vitamin D for prolonged steroid use - Endoxan 2mg/kg/d for 2-3M - 若Ab titers仍(+) after上述治療(約3M), 考慮繼續使用[(Predonine alone) or (predonine+AZA(1-2mg/kg/d)) or (predonine + MMF 2g/d)] for another 6M |
| Congo red and thioflavine-T negative(nonamyloid) fibrillar glomerular deposition diseases | 治療underlying, Immunosuppressions if idiopathic(?; unknown, no RCTs) |
| Fibronectin glomerulopathy | Unknown |
| Collagenofibrotic glomerulopathy | Unknown |
| Nail-patella syndrome | Supportive care; renal transplantation is preferred(因為不會recurrence) |
| Amyloidosis | 1.AL - Dara-CyBorD(daratumumab+bortezomib+cyclophosphamide+dexamethasone; ANDROMEDA NEJM 2021; PMID 34192431,現行一線〔PMID 34192431〕); 傳統Velcade-based C/T; autologous PBSCT(選擇性低風險者) 2.AA - Tx of underlying - Colchicine 0.6-2.0mg/d - 在FMF中的evidence: ↓disease progression, ↓proteinuria - Cytotoxic and immunosuppressive agents and biologic agents - Steroid, Endoxan, MTX, AZA, anti-TNFα, anti-IL6, anti-IL1... - Dimethylsulfoxide(DMSO) - anti-amyloid activity - Insufficient evidence - For renal amyloidosis - 可Renal transplantation - Graft survival is similar to general population - 20-33% recurrence renal amyloidosis after transplantation but graft loss due to amyloidosis is uncommon - 註:eprodisate(failed) 3.Dialysis related amyloidosis - Renal transplantation - After renal transplantation - Amyloid deposition(↓) soon - Bone cysts resolve slowly - Destructive spondyloarthropathy continues to progress !! - If HD kept - Biocompatible high-flux AK, use β2MG adsorbent column - Ultrapure dialysate - Consider HDF - Increase HD duration and frequency; consider SDHD or NHD - If PD kept - There are insufficient data to recommend a change in the dialysis modality - Doxycycline 100mg QD(inhibits amyloid formation and accumulation) - Reference:Benefit of doxycycline treatment on articular disability caused by dialysis related amyloidosis. (2013 Amyloid.) - Use in 3 Pts - Significant ↓articular pain, ↑passive and active movements though MRI showed no change of amyloid deposits - Consider OP(=清一清Amyloid...) - for shoulder pain - Arthroscopic or open surgery to remove synovium(infiltrated by amyloids) - for carpal tunnel syndrome - Debridement of the hypertrophied synovium(infiltrated by amyloids)不能只是transection of the transverse carpal ligament) - for bone cysts - Curettage and bone grafting of amyloid cysts - 可relieve pain and prevent pathologic fractures - for pathologic fractures - Prosthetic joints |
| MIDD | As AL的治療(雖然證據少) |
| Cast nephropathy | 1.As MM的治療(Velcade, thalidomide, lenalidomide better) 2.MYELOMA-II / EULITE 試驗後已不建議常規 TPE/HCO-HD,核心仍是 bortezomib-based 化療;僅選擇性考慮 if (urine LC>10g/24hrs or Cre>6 or oliguria) |
| TBMD/Alport's syndrome | 早期ACEi/ARB(EARLY PRO-TECT ramipril延緩進展〔PMID 32299679〕);SGLT2i(DAPA-CKD蛋白尿CKD支持治療〔PMID 32970396〕);轉診ENT助聽器;腎移植預後佳(de novo anti-GBM發生率約3%);TBMD多屬AD Alport光譜需長期追蹤蛋白尿與腎功能〔PMID 33094278〕 |
| Fabry's disease | 1.如果要給Enzyme replacement therapy, 要indefinitely - initiate early(可reverse end organ damage - give to all classical male Pts(including asymptomatic) - give to all Pts with CKD and ESRD(因為也要保護其他器官) - give to substantial non-renal manifestations - 若asymptomatic female carriers or males with atypical presentations (ie, with marginal levels of alpha-Gal A)-->case by case 2.For renal involvement |
| Treatment | |
| ERT | - Agalsidase alfa or beta at approved dose - Start ERT as soon as the definitive diagnosis has been made in patients with little or no residual enzyme activity - Start ERT as soon as the definitive diagnosis has been made in patients with residual enzyme activity if there is evidence of kidney involvement - ERT will not reduce proteinuria |
| Control of proteinuria | - Use ACE inhibitors and/or ARBs in addition to ERT - Titrate doses to achieve urine protein <500 mg/day, even if blood pressure <130/80 mmHg - Effects on progression are likely to occur only in the setting of optimal ERT dosing |
| Other therapy | - All other aspects of standard CKD care apply to the management of Fabry renal disease |
| - 可以renal transplantation; graft kidney可產生α-galactosidase A |
